

Payer contract negotiation is one of the few ways a practice can raise revenue without seeing another patient, yet most providers never learn how to do it. They spend years on clinical training and almost no time on the contracts that set what they get paid. That gap can cost a practice tens of thousands of dollars a year, and most of it is avoidable.
Key Takeaways
- Most commercial payers will negotiate, but only with a practice that shows up with data.
- Focus your ask on the handful of CPT codes that drive most of your revenue.
- Contract terms like timely filing and refund lookback periods can be worth as much as a rate increase.
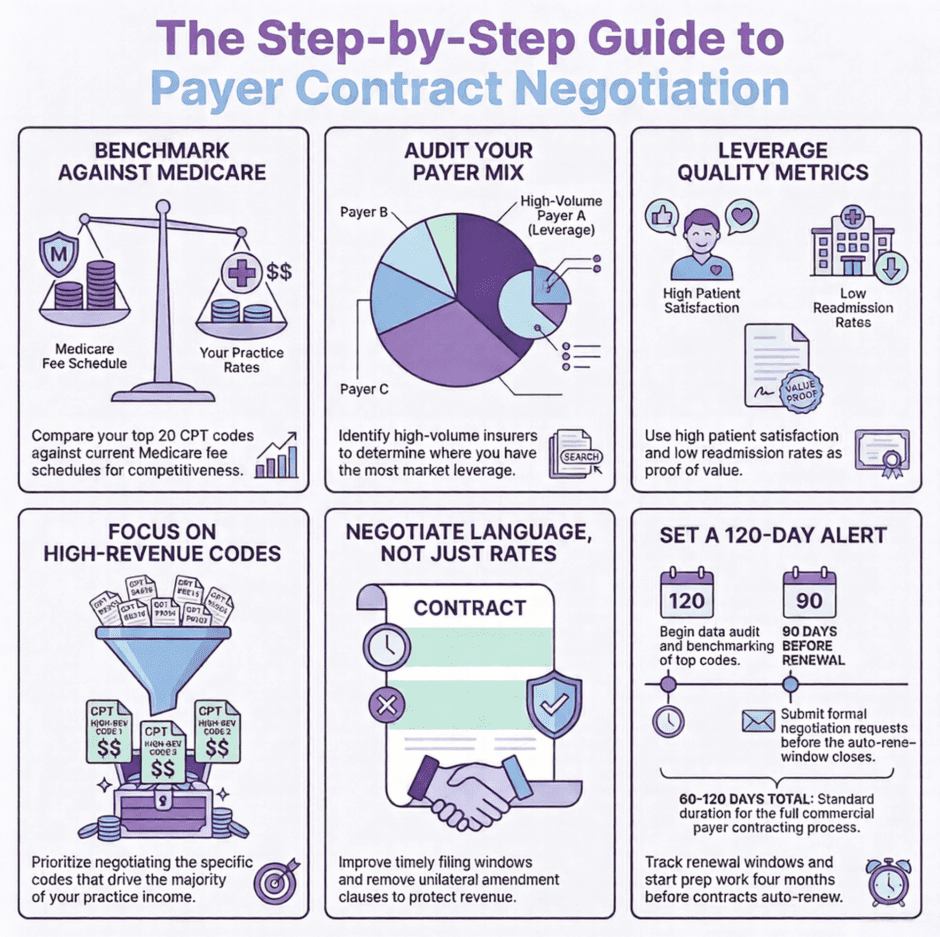
- Start preparing at least 120 days before a renewal window opens, or you may be stuck at the old rates for another year.
If you’re new to how these agreements work, start with the basics of payer contracting. This piece is about the negotiation itself, from setting your ask to knowing when to walk.
Why Providers Accept the First Offer
The pattern repeats across the country. Credentialing comes through, the payer sends a contract, and the provider signs it a day or two later without changing a word.
- Nobody taught them how. Contract negotiation isn’t part of medical school, and most practice managers have never had formal training in it either.
- They assume the rates are fixed. For most commercial payers that isn’t true, although getting movement takes knowing what to ask for and what you have to bargain with.
Payers also don’t publish what they pay other practices, so without doing some research a provider has nothing to push back with.
The result is a lot of practices on contracts that haven’t been touched in five or even ten years. Costs and patient volume went up. The rates stayed put.
What to Bring to the Table
 Walking into a negotiation without data is like walking into court without evidence.
At minimum, know what you’re paid today as a percentage of Medicare for your top 20 CPT codes. Most commercial payers set rates that way, and you can’t judge an offer without that number. Our guide to payer contract analysis walks through the benchmarking in detail, including how to use MGMA and other market data.
Then pull patient volume by payer. Payers care about market share, and a large share of their members coming through your door gives you bargaining power.
Bring quality data if you have it. Low readmission rates or strong patient satisfaction scores carry more weight every year as payers move toward value-based arrangements.
Setting Your Ask
Don’t ask for a blanket increase. Ask for specific rates on specific codes.
Start with the CPT codes that bring in the most revenue and set a target for each, expressed as a percentage of Medicare. A 5% increase on your top 10 codes will do more for the practice than a bigger increase spread across codes you rarely bill.
Know your floor before the first call. That’s the rate below which a code costs you money to deliver, and it’s the number that tells you when to stop negotiating.
Fee schedules vary widely by payer and region, so a target that makes sense with one payer may be unrealistic with another.
Running the Negotiation

Payers negotiate contracts every day and have a process for it. The conversation is usually less adversarial than providers expect.
Lead with numbers. “We’d like better rates” is easy to dismiss. “We’re paid 15% below comparable practices in this region on our top 10 codes, and here’s the comparison” is much harder to ignore.
Put your request in writing, with the codes, the current rates and the rates you’re asking for. It gives the payer’s contracting team something concrete to take through their internal review.
Expect a counteroffer. If the payer won’t meet your number on rates, that’s the moment to trade for better contract terms instead.
If they offer a multi-year agreement, ask for a built-in annual increase rather than a flat rate for the full term. A rate that looks fair in year one can be well under market by year three.
Terms Worth Negotiating Besides Rates
Some of the most valuable wins never show up on a remittance.
A longer timely filing window protects claims that get delayed. Shortening how far back a payer can demand refunds, for example on claims more than two years old, limits your exposure to recoupments. Removing unilateral amendment clauses stops the payer from changing terms without your agreement.
Dispute resolution language matters too. For wording that holds up in these conversations, see three phrases that protect you in payer contract negotiations.
When to Walk Away
 Not every payer is worth keeping at any price.
If a payer pays below your cost of care and won’t negotiate in good faith, ending the contract and steering patients toward better-paying plans may be the right call. Check your contract’s termination notice requirements before you decide, and look at how many of your patients that payer covers.
A payer that refuses to move this year isn’t always a lost cause, though. Document the refusal and come back at the next renewal with stronger data. Some payers respond after a few years of consistent quality numbers. Others never will, and learning which is which early helps you plan your payer mix.
Staying Ahead of Renewals
Most of the frustration with payer contracts comes from being reactive.
Many contracts renew automatically with no rate change unless one side acts within a set window, often 60 to 90 days before renewal. Miss it and you wait another year.
Put every contract on a calendar with its effective date, its renewal window and the date it was last renegotiated. Set a reminder at least 120 days before each window opens. That leaves time to pull your data, make the ask and get through the payer’s review before the deadline.
How Bargaining Power Differs by Specialty

Payer contracting looks different depending on your specialty, and a strategy that works for primary care may not carry over to a surgical group.
Specialists who perform high-cost procedures usually have more room to negotiate, because the dollars at stake are larger for both sides. A cardiology practice negotiating cath lab rates is having a very different conversation than a family medicine practice negotiating E/M codes. Low-volume, high-cost services work the same way. A payer may have few in-network options for them, and that scarcity works in your favor.
Primary care’s bargaining power usually comes from volume and from how many of the payer’s members you manage.
Behavioral health is its own case. Rates there have historically lagged other specialties, and parity enforcement is uneven, but network adequacy requirements can work in the provider’s favor. Behavioral health payer contracting covers that side in more depth.
State and federal rules also shape what a payer can and can’t do in a negotiation. See the laws that govern payer contract negotiations for the specifics.
Payer Negotiation FAQ
Can a small practice negotiate better reimbursement rates?
Yes, but the bargaining points are different. A small practice can lean on its specialty, its quality outcomes, its location or the payer’s network adequacy obligations. Volume isn’t the only card at the table.
How do I know if my rates are below market?
Compare your contracted rates to the current Medicare fee schedule for your top CPT codes. MGMA survey data and conversations with peers in your specialty can show roughly where you stand.
What should I ask for in a rate negotiation?
Ask for specific rates on your highest-revenue CPT codes, expressed as a percentage of Medicare, and back each one with data. Specific requests get further than a general request for higher rates.
How long does a rate renegotiation take?
A renegotiation during a renewal cycle usually takes 30 to 60 days, depending on the payer.
What happens if I never renegotiate my payer contract?
Your rates stay flat while your costs rise, and the gap between what you’re paid and what care costs to deliver keeps widening.
How Medwave Helps With Payer Negotiations

Medwave handles rate negotiations and payer contracting for practices that don’t have the time or the data to do it themselves. We benchmark your current rates, build the ask and work it through the payer’s review, and we track your renewal windows so a contract never rolls over without a look.
When Medwave also handles a practice’s medical billing, the negotiation starts from what each payer is paying on your claims today, not from the contract alone. That makes underpayments and below-market codes easier to spot. It also means a new rate gets checked against the remittances that follow, so you know it was applied correctly.

Co-Founder and COO of Medwave, bringing more than 25 years of hands-on experience in healthcare revenue cycle management, payer contracting, and medical credentialing.