

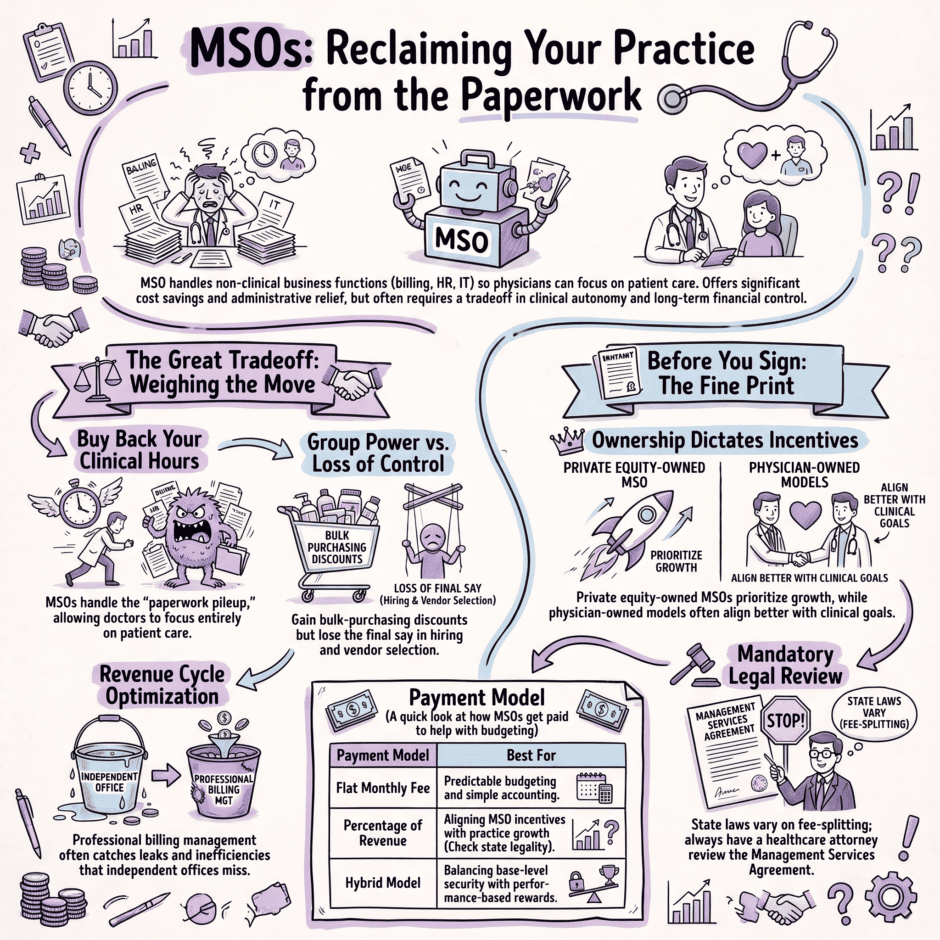
A management services organization (MSO) takes over the business side of a private practice, from payroll and billing follow-up to HR and vendor contracts, so physicians can spend their hours on patients instead of spreadsheets.
The pitch is easy to like. Whether it works for your practice comes down to the management services agreement behind it, and that document deserves more scrutiny than most physicians give it. Before you sign, learn how these organizations charge and who owns them, then read the fine print with an attorney.
Key Takeaways
- An MSO handles the non-clinical side of a practice, such as billing, HR, marketing, and credentialing, while physicians keep control of patient care.
- MSOs charge flat fees, tiered packages, a percentage of revenue, or a hybrid, and state law often decides which of those are legal.
- Who owns the MSO shapes its incentives. Physician-owned, private equity-owned, hospital-affiliated, and joint venture models all behave differently.
- The trade is lower admin burden and purchasing power in exchange for some loss of control and long-term contract risk.
- Have a healthcare attorney review any Management Services Agreement before you sign.
What is an MSO and What Does It Do for a Practice?
 A Management Services Organization runs the operational and financial side of a medical practice. It doesn’t practice medicine, and it doesn’t make clinical decisions.
The services list is usually long. Revenue cycle management (coding, claims, and collections) is one of the most common. Many MSOs also cover HR, payroll, marketing, IT and EHR support, office space, vendor relationships, and credentialing and payer contracting.
The model exists largely because of Corporate Practice of Medicine (CPOM) laws. Many states bar non-physicians from owning or controlling a medical practice so financial interests can’t override patient care. An MSO gives investors and administrators a legal way into the business side of a practice, provided licensed providers keep clinical judgment.
Because one MSO serves many practices, it can often get better pricing on supplies, software, and services than a single office could. That’s the theory. How well it holds up depends on the MSO and on how many other practices are competing for its attention.
Why Practices are Looking at MSOs Now
Overhead keeps rising while reimbursement stays flat, and that squeeze is sending more independent physicians in search of outside help. Administrative staff are harder to hire and keep, and the regulatory workload grows every year. For many doctors, the appeal of an MSO has little to do with giving up control. They want back the hours that disappear into vendor calls and denied claims.
Career stage plays a part too. Physicians close to retirement sometimes treat an MSO relationship or a roll-up as a route to selling the practice at a fair price. Younger physicians may want a lighter admin load early on so they can build patient volume.
If cost pressure is the main driver, pause before restructuring anything. The fix is sometimes closer to home, like tightening your billing process or renegotiating a stale payer contract.
How Do MSOs Get Paid?
 There’s no single pricing model. Which one makes sense depends on your specialty, your patient volume, and what your state allows.
A flat monthly fee is the simplest. Budgeting stays predictable, though the fee can feel heavy in a slow month.
Tiered packages let you pay only for the services you use, so a practice with its own HR person isn’t paying for HR support.
Percentage-of-revenue deals tie the MSO’s pay to what your practice collects. Some states restrict or prohibit them over fee-splitting and anti-kickback concerns, so never assume this option is open to you.
Hybrid models pair a base fee with a performance component.
Whatever you’re offered, bring in a healthcare attorney before signing. Rules on revenue sharing, self-referral, and CPOM vary from state to state, and a contract that’s fine in one state can create real liability in another.
How MSOs are Owned and Structured
Ownership shapes how an MSO behaves, so find out who’s running it before you sign anything.
Physician-owned MSOs are built and run by doctors. You may still give up some day-to-day control, but the incentives tend to stay close to patient care.
Private equity-owned MSOs answer to investors who expect a return. That doesn’t guarantee bad outcomes for patients. It does put growth and profit near the top of the list, sometimes higher than a physician owner would put them.
Hospital-affiliated MSOs plug a practice into a health system’s administrative infrastructure. Referrals and shared resources can get easier, but expect a nudge toward the system’s preferred vendors, EHR platform, and referral network.
Joint venture MSOs spread ownership and risk across several parties. They work when everyone’s incentives line up and get messy fast when they don’t.
The financial design varies as well. A service-fee MSO charges a flat rate or percentage for its work. A cost-plus MSO passes its operating costs to you with a markup on top. An equity-based MSO gives physicians a stake in the management company, which brings upside if it performs and ties part of your finances to decisions you may not control.
One more distinction carries a lot of weight. Some MSOs only sell services, and your practice stays independent. Others buy your equipment or real estate and lease it back, so you still see patients under your own name without owning the assets your practice runs on. Physicians tend to underestimate that second arrangement until they’re a few years into it.
What Belongs in a Management Services Agreement?
 The Management Services Agreement (MSA) sets out what the MSO will do, what you’ll pay, and how either side gets out. Give it the attention you’d give a mortgage.
Start with fees, then push for specific performance metrics tied to the services you’re paying for. If the MSO takes a share of revenue, it should be able to show it’s improving results beyond what your practice would manage alone.
Scope needs detail. A promise to “handle administrative functions” isn’t a scope. Termination terms deserve equal weight, because some MSAs carry penalties steep enough that leaving hurts even after the relationship has clearly failed.
If the deal includes selling assets or equity, get an independent valuation first. MSOs, especially private equity-backed ones, have every reason to value your practice at the lowest number they can defend. Hire a healthcare attorney who has reviewed MSAs before. A general business attorney isn’t the right fit for this one.
Where an MSO Can Help a Practice
When the fit is right, an MSO can change how a practice runs day to day.
Group purchasing brings down what you pay for equipment, supplies, and software. Compliance support usually improves as well, since MSOs track HIPAA, Stark Law, and billing rule changes as part of their core business.
A well-run MSO can also tighten billing and collections and spot leaks a busy practice never had time to look for. Modern IT and analytics tools often come bundled in at a fraction of what they’d cost to buy and maintain on your own.
Then there’s time. Fewer administrative fires mean more hours with patients. For practices planning an eventual sale, an MSO or roll-up can also bring in buyers who wouldn’t otherwise look.
The Downsides Worth Weighing
 Each of those benefits has a cost, and it’s often bigger than it looks at signing.
Loss of control is the complaint you’ll hear most from physicians who regret joining. Depending on the structure, you can lose say over hiring, vendor choices, and how your own front office runs.
Fees can outrun the value. Paying a markup for services you’d never have bought yourself eats into the savings the MSO promised. Some agreements also require MSO-chosen vendors, including a specific EHR or equipment supplier, whether or not they suit your workflow.
Conflicts of interest need a hard look, particularly under private equity or hospital ownership. Their financial goals won’t always match your clinical priorities, and when the two collide in a dispute, the contract usually favors whoever wrote it.
Long terms can lock in conditions that made sense five years ago and no longer fit where the practice is going. When the MSO employs your staff directly, morale and retention can also slip under a numbers-first culture that clashes with how you’ve always run your team.
Red Flags That Should Make You Walk Away
Most warning signs show up early if you’re looking for them.
Be wary of a contract with no room to negotiate terms, and of vague or missing performance metrics. An MSO that can’t show you its track record with other practices is telling you something.
An offer that sounds far better than anything else on the market deserves a direct question about why. Long terms with no realistic exit, steep early-termination penalties, and a lowball valuation of your practice are all reasons to call an attorney before going further.
Your clinical autonomy needs as much protection as your finances. No MSA is worth signing if it quietly hands away the way you practice.
Here’s a side-by-side look at the tradeoffs.
| Advantages of Joining an MSO | Disadvantages of Joining an MSO |
|---|---|
| Group purchasing power lowers costs on equipment, supplies, and software | Fees can outpace the value delivered, especially for services you wouldn’t have chosen on your own |
| Stronger, more current compliance support for HIPAA, Stark Law, and billing rule changes | Vendor and EHR choices may be dictated by the MSO instead of your practice |
| Tighter revenue cycle management can improve cash flow and catch missed inefficiencies | Financial goals of the MSO, particularly under private equity or hospital ownership, may not match your clinical priorities |
| Access to modern IT systems and analytics at a fraction of independent cost | Long-term contracts can lock in terms that stop fitting your practice a few years in |
| More physician time back for patient care instead of administrative tasks | Loss of control over hiring, vendors, or daily operations, depending on the agreement |
| Can open doors to a stronger sale price or exit down the road | Staff hired directly by the MSO may see lower morale under a numbers-first culture |
Is There a Middle Ground Between Independence and an MSO?
 Plenty of practices don’t need the full MSO package. Some administrative problems call for a lighter fix.
Outsourcing specific functions like billing, credentialing, or payer contracting to a specialist gets you much of what an MSO offers without handing over staffing, vendors, or long-term strategy. You bring in expertise where the practice needs it and stay as independent as you were.
That’s often the smarter first step for practices whose biggest headaches are denied claims, credentialing delays, or payer contracts nobody has renegotiated in years. Fixing those rarely requires giving up equity or signing a multi-year MSA with an exit penalty attached.
MSO FAQ for Private Practices
Is joining an MSO the same as selling my practice?
Not necessarily. Some MSOs simply charge for administrative services while your practice stays fully independent. Others do purchase equipment, real estate, or a share of the business, which changes ownership in ways that go beyond a basic service arrangement. Read the structure carefully before assuming either scenario applies to your situation.
Can an MSO legally take a percentage of my practice’s revenue?
It depends on your state. Some states allow percentage-based fee arrangements, while others restrict or prohibit them due to fee-splitting and anti-kickback concerns. A healthcare attorney familiar with your state’s rules should confirm what’s actually permitted before you agree to a percentage-based deal.
Will an MSO control who I hire and fire?
It can, depending on the structure. Some MSAs give the MSO direct authority over staffing decisions, particularly if they employ your front office or clinical support staff directly. Ask this question explicitly before signing, since it isn’t always spelled out clearly in marketing materials.
How long do MSO contracts typically last?
Terms vary widely, and that’s exactly why they need close review. Some agreements run for multiple years with automatic renewal clauses and significant penalties for early termination. Before signing, make sure you know the exit path and what it would cost you to leave if the relationship doesn’t work out.
What’s the difference between a physician-owned MSO and a private equity-owned one?
Physician-owned MSOs are run by doctors, which tends to keep clinical priorities closer to the center of decision-making. Private equity-owned MSOs answer to investors focused on growth and returns, which can create pressure that occasionally works against a physician’s clinical goals. Neither structure is automatically right or wrong, but the incentives behind each one are worth knowing upfront.
Where Medwave Fits If You Stay Independent
 Medwave works on the parts of a practice that most often push physicians toward an MSO in the first place, and leaves the rest in your hands. Our medical billing team works claims and collections so revenue stops leaking through denials and slow follow-up. Our credentialing specialists keep providers in-network and billable, and our payer contracting team reviews and renegotiates terms so your rates reflect the work you do.
If you’re still weighing an MSO offer, fixing these first puts you in a stronger negotiating position whichever way you decide.
Send us a note below and we’ll look at where your practice stands.

Co-Founder and COO of Medwave, bringing more than 25 years of hands-on experience in healthcare revenue cycle management, payer contracting, and medical credentialing.