

Rate negotiation is the process of asking a payer to raise what it pays for your services, using your own collection data, what comparable practices are paid, and what the care costs you to deliver. Payers expect to hear from practices that have done that work, and they rarely volunteer increases to the ones that have not. Medwave handles rate negotiation for practices that would rather spend their time on patients, from the first contract analysis through the signed amendment.
Key Takeaways
- Commercial rates for physician services vary widely by specialty, from about 110% of Medicare or less in family medicine to 250% or more in emergency medicine, so a rate only looks low or high next to your own specialty.
- Start talks 90 to 180 days before the renewal date, because asking in the final weeks leaves you with no room to walk away.
- Build the ask around the few CPT codes that carry most of your revenue, backed by collection data for each payer.
- Terms such as the timely filing window, the refund lookback, and how the fee schedule updates can be worth as much as the rate itself.
How Payers Set What They Pay You
 Every contract pays from a fee schedule, and the first thing to learn is which kind yours uses. Many are written as a percentage of the Medicare Physician Fee Schedule, so the payer’s rate moves whenever Medicare’s does. Others use a schedule the payer owns and updates on its own timetable, or one frozen at the values of a past year. Each behaves differently over a multi-year term, which is why the update clause deserves as much attention as the dollar amounts. Our overview of medical provider fee schedules covers how they compare.
Medicare is a moving baseline. For 2026 the conversion factor is $33.40 for most clinicians and $33.57 for qualifying Advanced APM participants, and CMS describes part of the increase as a one-year 2.50 percent update stipulated by statute, according to the CMS final rule fact sheet. A contract pegged to the current Medicare schedule will follow whatever Medicare does next, and one pegged to a frozen schedule will not.
What Commercial Payers Pay Compared With Medicare
Benchmarking works best as a percentage of Medicare for each CPT code, because that puts every payer and every code on one scale. A 2021 Urban Institute study of professional services found that the markup over Medicare depends heavily on specialty.
- Family medicine, OB/GYN, dermatology, ophthalmology, and psychiatry averaged about 110% of Medicare or less.
- Nine specialties, including gastroenterology, cardiology, general surgery, and orthopedics, averaged between 120% and 150%.
- Radiology averaged 180% and neurosurgery 220%.
- Emergency department and critical care specialties averaged 250%, and anesthesia 330%.
Those are national averages from one study, so they show where a specialty usually sits and not what a particular payer in your market will pay. Your own contracts are the better evidence.
There is also a free comparison source. Under the federal Transparency in Coverage rule, most group health plans and insurers have posted machine-readable pricing files, including in-network negotiated rates, since July 1, 2022, as described on the CMS health plan price transparency page. The files are large and awkward to read, but they show negotiated rates by billing code.
Building the Case Before You Ask
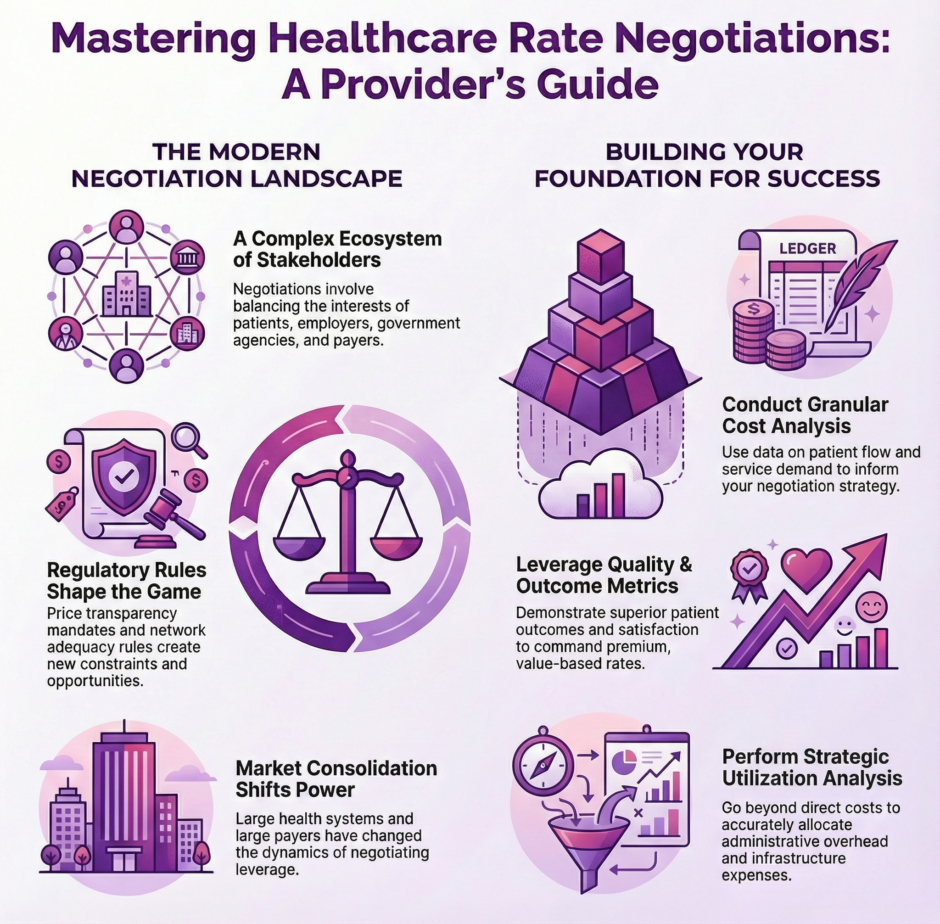
 The strongest requests arrive with four numbers for each payer. Those are what you collect on your top codes, what that equals as a percentage of Medicare, what the service costs you to deliver, and how many of that payer’s members you see. Billed charges tell you little here, since you set them yourself, and the gap between charges and payment is explained in our FAQ on contracted rates versus billed charges.
Cost data sharpens the ask. Clinical time and supplies are easy to count, while overhead has to be allocated, so use the same allocation method for every service you compare. Where a payer’s rate falls below your cost for a service, put the figure in the request. Payers also weigh outcomes and access, and the shift toward value-based care makes those numbers more relevant each year.
A worked example shows why the effort pays. If a practice sees 25 patients a day, five days a week, and all of those visits fall under contracts it renegotiates, an extra $10 per visit adds $1,250 a week, or $65,000 a year.
Before you build the file, run the current agreement against our payer contract negotiation checklist. Our guide to payer contract analysis covers what to pull from the contract itself.
When to Start and How the Talks Run
The best window opens 90 to 180 days before the renewal date. That gives the payer time to review the request without a deadline forcing a quick no. Other natural openings come when you first join a network or add providers, locations, or services. A competing practice leaving a payer’s network also helps you, since the access gap lands on the payer. How long contracting takes by payer type is laid out in how long payer contracting takes, which helps you pick a start date.
- Pull the current contract and read the renewal, termination, and fee schedule update terms.
- Build a data file for each payer and rank your CPT codes by revenue.
- Send a written request with target rates and supporting data to the payer’s contracting representative.
- Answer the counteroffer code by code, since a blended percentage can hide cuts on the codes that matter most.
- Escalate in writing if talks stall, and model what leaving that payer would cost before deciding how firmly to hold your position.
For tactics inside the negotiation itself, see our guide to payer contracting and negotiation strategies. Leaving a network is rarely the first move and is sometimes the right one, and our comparison of in-network versus out-of-network contracting shows what the numbers look like by specialty. The federal and state laws that govern payer contract negotiations explain what each side may do, including the antitrust limits on groups of practices negotiating together.
Contract Terms Worth Negotiating Besides the Rate
A rate is one line in a contract with many others that move money.
- The timely filing window, since a longer window cuts write-offs on late or reworked claims.
- The refund and overpayment lookback period, which limits how far back a payer can recoup.
- How the fee schedule updates, including whether the rate follows the current Medicare schedule.
- The effective date of the new rates, with a request that they apply from the date talks began.
- Termination and notice terms.
A small rate gain paired with a short timely filing window can cost more than it earns, because a claim filed late may not be paid at all.
After the New Rates Are Signed
A signed amendment only matters if the payer pays it. Load the new schedule into the practice management system, then check the first remittances against it. Underpayment can appear when a payer’s system is slow to update, and it can appear later as schedules change without notice, which we cover in fee schedule drift. Put the next renewal date on the calendar with the 180-day mark flagged, since that is when preparation for the next round should begin.
Rate Negotiation FAQs
What is rate negotiation in healthcare?
Rate negotiation is the process of asking a payer to raise the fee schedule, or the percentage of Medicare, that it pays for your services. The request rests on your collection data, market benchmarks, and costs, and it happens at renewal, when you join a network, or when your practice changes.
Can a small practice negotiate rates with insurance companies?
Yes. Payers negotiate with practices of every size. A small practice’s strength comes from its data, the number of that payer’s members it sees, and any gap in access it fills, so preparation matters more than practice size.
When is the best time to negotiate rates?
Start 90 to 180 days before the contract renewal date. Other good moments come when you first join a network, add providers or locations, or when a competing practice leaves the network.
How do I know if my rates are below market?
Convert what each payer pays on your top CPT codes into a percentage of the Medicare fee schedule, then compare it with the benchmarks for your specialty and with your other payers. Payer machine-readable pricing files add a view of negotiated rates by code.
What happens if a payer refuses to raise my rates?
Move to the other terms in the contract, such as timely filing, refund lookback, and the fee schedule update clause. Escalate in writing, model what leaving that payer would cost, and give proper termination notice if leaving is the right call.
What does Medwave do in a rate negotiation?
We analyze your current contracts and financial performance, build a strategy for each payer, and handle the discussions and paperwork through contract execution, with regular updates to your leadership team.
Medwave at the Table With Your Payers
 Medwave has supported more than 15,000 providers with credentialing, contracting, and billing, and rate negotiation connects to both of the other services. Our payer contracting work covers new and existing agreements, and our medical billing team sees what each payer actually pays, which is the evidence behind the next request.
Adding a provider is one of the natural moments to revisit rates, and the new clinician cannot bill under the contract until credentialing is complete. Our medical credentialing team handles the enrollment side, so the rate request and the provider’s start date can be planned together.
Practices that want to see where they stand before committing to anything can book a consultation and bring a recent fee schedule or a few remittances.
Send us your contract and your top ten CPT codes by revenue, and we’ll show you where your rates sit against Medicare.