

Payer contracting determines what a practice earns on each claim for the length of the agreement, which is often several years. Medwave negotiates and manages payer contracts for practices of any size, and the team has supported 15,000+ providers. Our work runs from the first network request through the rate conversation and into the audits that confirm the payer pays what the contract says.
Key Takeaways
- Most providers wait two to six months from application to an effective contract. Medicare enrollment sits at the short end and large national carriers at the long end.
- Every proposed rate should be compared with the Medicare fee schedule and the payer’s current fee schedule on your top billed codes before negotiation starts.
- Auto-renewal, unilateral amendment, and most-favored-nation clauses can cost more over a multi-year term than a slightly low starting rate.
- A signed contract needs scheduled reviews, since payers revise fee schedules and policies after signing.
What’s Payer Contracting?
 Payer contracting is the process of negotiating and signing participation agreements between a healthcare provider and an insurance company or other payer. Each agreement sets which services the provider delivers to the payer’s members, what the payer reimburses for them, and the rules both sides follow on claims, audits, and disputes.
Credentialing and contracting usually run side by side. Credentialing is the payer’s verification of your licenses, training, and malpractice history. Contracting is the business agreement that sets rates and terms. A provider can clear credentialing and still be negotiating, or agree to terms and still be waiting on verification, so both files need to be tracked together.
Medicare works differently. Providers enroll through PECOS and accept the published fee schedule, which leaves no rates to negotiate.
Payer Contracting Timelines by Payer Type
Timelines depend mostly on who sits on the other side of the application. These ranges assume a clean submission, and our guide to payer contracting timelines breaks down each one.
- Large national commercial carriers such as Blue Cross Blue Shield plans, UnitedHealthcare, Aetna, and Cigna usually take four to six months.
- Regional commercial plans usually take three to five months.
- Managed care plans, including HMOs, narrow networks, and Medicaid managed care organizations, usually take three to four months.
- Medicaid runs from two to six months depending on the state.
- Medicare enrollment through PECOS usually finishes in two to three months.
One missing document can push the first billable date back by a month or more. An incomplete application adds four to eight weeks on its own, and a payer’s committee meeting schedule can add another one to three months. Complete documentation and quick answers to payer requests keep an application moving. A weekly status follow-up catches a stall before it costs a month.
If an application has stalled or a payer has gone quiet, book a consultation and send us the details.
The Six Stages of the Payer Contracting Process
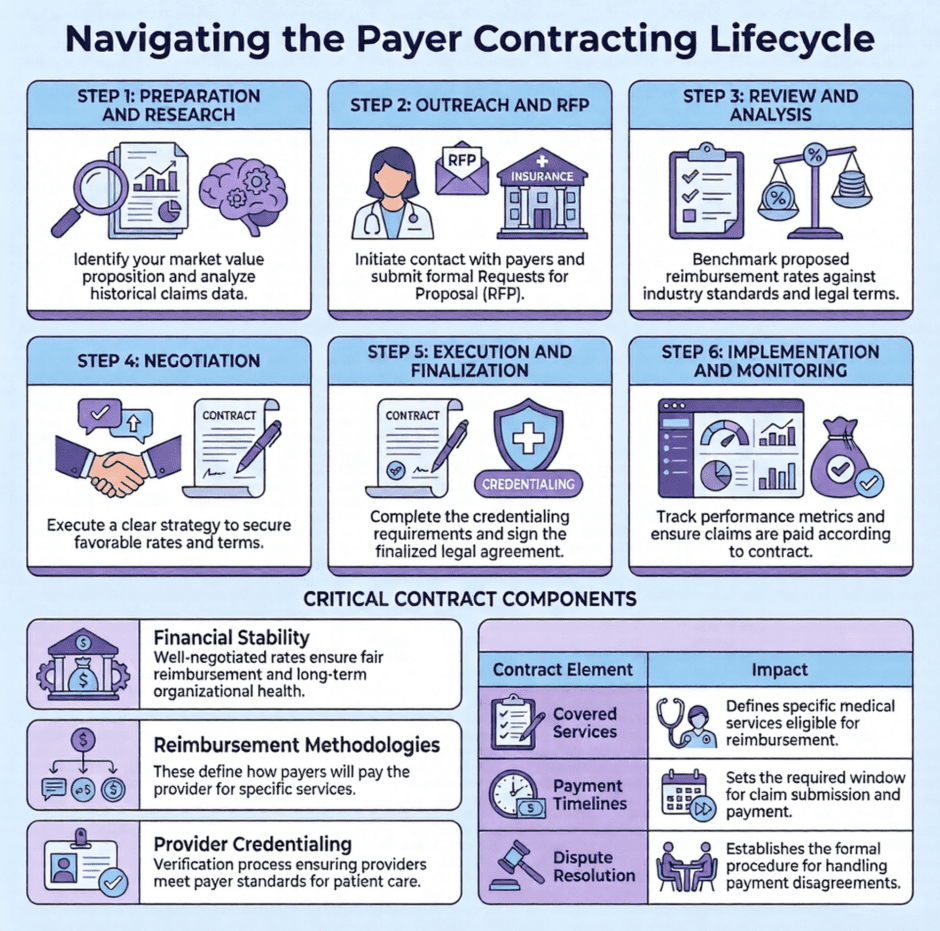
Skipping a stage usually shows up later as a weak rate or a missing protection.
- Preparation and market research. Claims history by CPT code, payer mix, and current collections by payer get compared with market rates for your specialty and region.
- Initial outreach and request for proposal. The application or network request goes to the payer, and the first answer to find is whether the panel for your specialty is open, closed, or limited.
- Contract review and analysis. Every clause is read against a checklist covering rates, filing limits, payment timelines, renewal terms, and termination rights.
- Negotiation. Rates and protective language are negotiated with the payer directly, and the tactics are covered on our rate negotiations page.
- Contract finalization and execution. The effective date and the fee schedule attached to the agreement are confirmed before anyone signs.
- Implementation and ongoing monitoring. Paid claims are checked against the contracted fee schedule, and renewal and notice dates go on a calendar.
What to Check in a Payer Contract Before You Sign
A contract that looks fine on headline rates can still lose money once payment terms and administrative requirements are counted. These checks apply to a new contract and to a renewal.
- Rates on your top 20 billed CPT codes by volume, compared with the Medicare fee schedule as a baseline.
- Whether rates are a flat fee, a percentage of billed charges, or a percentage of Medicare, and the date they take effect.
- Timely filing limits for initial claims, corrected claims, and appeals.
- Prompt payment terms and interest penalties for late payment.
- Auto-renewal clauses and the notice period needed to opt out.
- Unilateral amendment language that lets the payer change rates without your agreement.
- Termination without cause, and most-favored-nation clauses that limit future negotiation.
- Language that covers CPT codes added after signing and protects against post-authorization denials.

Run any agreement through our payer contract negotiation checklist before you sign, and note that we flag three protective phrases in every contract review. For the financial side, our guide to payer contract analysis shows how to compare contracts on profit per claim after administrative cost.
State and federal rules limit what a payer can put in an agreement. Prompt payment deadlines, any-willing-provider laws, and No Surprises Act provisions all vary by state or by plan type, and our overview of the laws that govern payer contract negotiations covers where they apply. For benchmarking beyond Medicare, Milliman publishes commercial reimbursement benchmarking against Medicare fee-for-service rates.
Where Providers Lose Ground in Payer Contracting
Even well-run practices hit the same obstacles.
- Negotiating fair reimbursement rates against a payer with far more market power than the practice.
- Getting past closed insurance panels.
- Spotting auto-renewal and unilateral amendment language in dense agreements.
- Meeting quality targets under value-based care models.
- Tracking fee schedules and renewal dates across many contracts with contract management that rarely gets staff time.
Some practices ask whether staying out of network would pay better. Our comparison of in-network and out-of-network contracting by specialty models that tradeoff.
Where Payer Contracting is Headed
Risk-sharing arrangements and value-based purchasing programs are pushing more quality targets into contract language. Payers are also exchanging more data with providers, which ties contract performance to interoperability. Artificial intelligence is also entering contract analysis and negotiation. Contracts signed now will be measured against those expectations at renewal.
Payer Contracting FAQs
How long does payer contracting take?
Most practices wait two to six months from application to an effective contract. Medicare enrollment through PECOS usually takes two to three months, large national commercial carriers take four to six, and Medicaid ranges from two to six depending on the state. An incomplete application adds four to eight weeks by itself.
What is the difference between credentialing and payer contracting?
Credentialing is the payer’s verification of a provider’s licenses, training, and malpractice history. Payer contracting is the agreement that sets reimbursement rates and the terms of network participation. The two usually run at the same time, and either one can finish first.
Can a provider negotiate rates with Medicare?
No. Medicare publishes its fee schedule, and providers enroll and accept it as written. Rate negotiation applies to commercial and managed care plans.
What should be reviewed before signing a payer contract?
Check the rates on your top billed CPT codes against the Medicare fee schedule, the timely filing and prompt payment terms, auto-renewal and notice periods, unilateral amendment and termination clauses, and any most-favored-nation language. Each item is in the download checklist linked above.
What can a provider do when a payer panel is closed?
A closed panel means the payer is not adding providers in a specialty or area, usually because it considers the network full. Providers can document a genuine gap in the network, ask about exception or limited-network pathways, and reapply when the panel reopens. Our guide on getting into a closed payer panel covers the steps.
How much does payer contracting cost with Medwave?
Payer contracting is priced per provider, with volume discounts and group rates available. Every quote follows a review of the practice’s needs.
What Medwave Does with Your Payer Contracts
 Medwave handles payer contracting for healthcare providers from the first network request through ongoing contract management, and we stay with a client until their applications and contracts are complete. One team tracks the credentialing file and the negotiation together, which keeps a signed contract from sitting unused while a verification step finishes.
Contract terms feed directly into medical billing, because the fee schedule attached to each agreement is what claims get paid against. We tie every contract to your revenue cycle management, so rate changes and underpayments show up where your team already looks. Pricing details are on our pricing page.
Send us the payer contract that’s giving you trouble, or tell us which payers you want to add, and we’ll take it from there.