


Every practice eventually asks the same question. Should we sign with this payer, or stay out-of-network? It sounds like a simple yes or no. It isn’t. The right answer depends on your specialty, your patient volume, your local market, and how much of your revenue comes from a handful of large payers versus a wide mix of smaller ones.
Too many practices treat in-network vs. out-of-network contracting as a one-time decision made at credentialing and then forgotten. That’s a mistake. It’s a financial model that needs revisiting every year, and the right answer for a primary care group is often the wrong answer for a plastic surgery practice down the street.
This guide breaks down how the revenue math actually works for each side of the decision, why specialty changes everything, and how to build a model that tells you which path pays more before you sign anything.
Key Takeaways
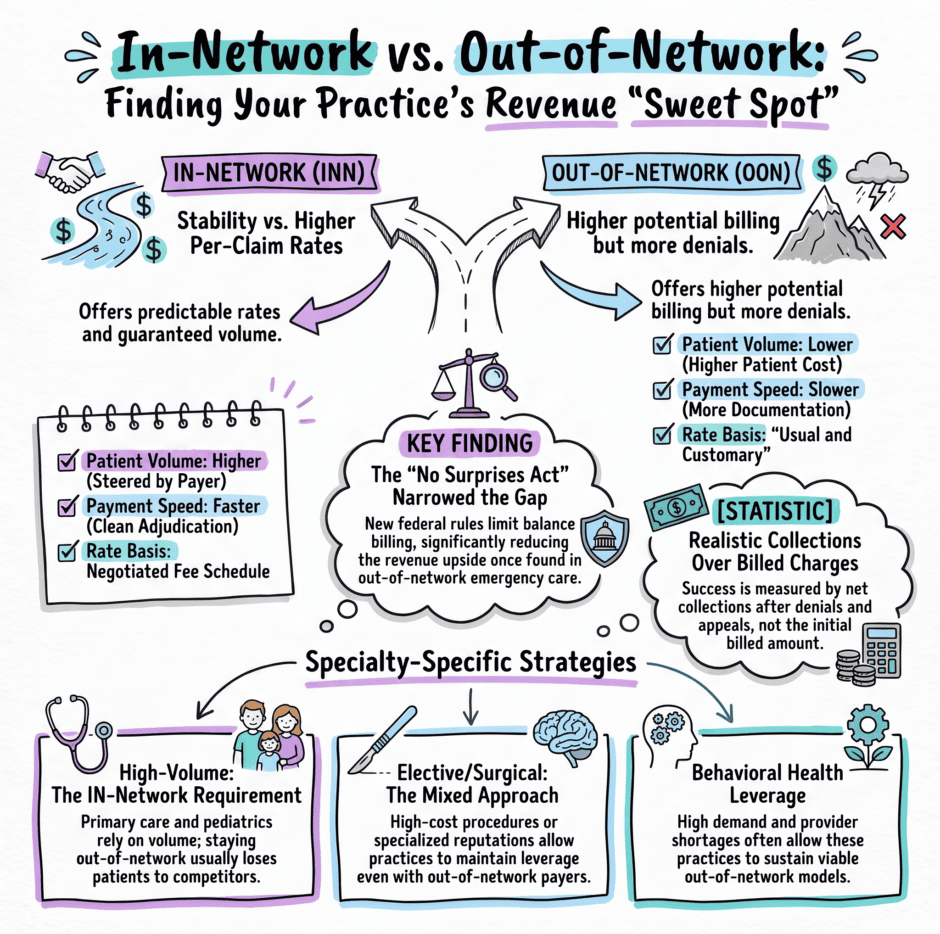
In-network contracting trades a lower, negotiated rate for guaranteed patient volume and predictable collections. Out-of-network contracting can produce higher per-claim reimbursement, but it comes with more denials, slower payment, patient responsibility for balance billing (now limited by the No Surprises Act), and smaller patient pools. Healthcare specialties with high patient volume and thin per-visit margins, like primary care, usually do better in network. Specialties with fewer, higher-cost procedures, like certain surgical or elective fields, sometimes do better out of network, but only in specific market conditions. The right call requires a real revenue model, not a gut decision.
What In-Network and Out-of-Network Contracting Mean
 In-network contracting means your practice has signed a participation agreement with a payer. You agree to accept their fee schedule as payment in full, and in exchange, the payer steers its members toward you. Patients pay lower copays and coinsurance to see you, which usually means more of them will choose to.
Out-of-network means you haven’t signed that agreement. You can still see the payer’s members, but reimbursement rates aren’t fixed by contract. Patients typically face higher out-of-pocket costs, and in many cases, insurers pay a smaller share of the bill directly to you.
Neither status is inherently better. Each one shifts risk and reward in a different direction, and the shift lands differently depending on what kind of care you provide.
How the Revenue Math Differs Between the Two Models
Fee Schedules vs. Billed Charges
In-network, you’re paid off a negotiated fee schedule, usually tied to a percentage of Medicare rates or a custom rate card built during contract talks. It’s lower than your billed charge, but it’s known in advance. You can forecast revenue per visit with real accuracy.
Out-of-network, you bill your full charge. Payers reimburse based on their own calculation of “usual and customary” or a percentage of an allowed amount, and that number can vary widely by payer, by plan, and sometimes by claim. Some claims get a fair reimbursement. Others get cut down hard, with the balance shifted to the patient, subject to current balance billing rules.
Collection Rates and Write-Offs
This is where a lot of practices get surprised. In-network claims tend to have cleaner adjudication and fewer denials, because the contract terms are already agreed upon. Out-of-network claims see higher denial rates, more requests for medical necessity documentation, and slower turnaround.
A high reimbursement rate on paper means very little if half those claims get denied, appealed, and partially paid six months later. Model your realistic collection rate, not your billed rate, when comparing the two paths.
The No Surprises Act’s Effect on Out-of-network Revenue
Federal balance billing protections changed the out-of-network calculation substantially for emergency care and for many non-emergency services at in-network facilities. Patients in covered situations can no longer be billed the difference between your charge and what insurance pays. Instead, disputes route through a federal independent dispute resolution process.
This matters a great deal for specialties like anesthesiology, emergency medicine, and radiology, where out-of-network billing used to generate meaningfully higher revenue per encounter. That upside has narrowed. Any revenue model built on pre-2022 out-of-network assumptions is out of date and needs to be redone.
Why the Tradeoff Isn’t the Same Across Specialties
Primary Care and High-volume Specialties
Primary care, pediatrics, and other high-frequency, lower-cost-per-visit specialties depend on volume. Patients choose a provider based heavily on which ones their plan covers at the lowest cost. Staying out of network in these fields usually means losing patients to in-network competitors, not charging them more.
For these practices, in-network status is close to a requirement, not a choice. The real work is negotiating the best possible rate within that network relationship, not deciding whether to join it.
Procedure-heavy and Elective Specialties
Fields like certain cosmetic and elective surgical specialties, some dermatology services, and select orthopedic procedures behave differently. Patients researching these services often shop around regardless of network status, and the per-procedure revenue is high enough that a smaller out-of-network patient pool can still produce strong total revenue.
These practices sometimes maintain a mixed strategy: in-network for high-volume payers in their region, out-of-network or single-case-agreement based for others, especially where their reputation or specialization gives them leverage patients are willing to pay for.
Behavioral Health and Telehealth
 Behavioral health sits in an unusual spot. Demand is high, network adequacy requirements for payers are under increasing regulatory pressure, and many markets have real shortages of in-network providers. That shortage sometimes gives behavioral health practices leverage to negotiate stronger in-network rates than other specialties get, or to sustain a viable out-of-network model because patients have few other options and often submit claims for partial reimbursement themselves.
Telehealth adds another variable. Reimbursement parity rules vary by state, and payer telehealth fee schedules don’t always match in-person rates, which changes the in-network math on a state-by-state basis.
Building a Revenue Model Before You Decide
Payer Mix and Patient Volume
Start with your actual payer mix. Pull twelve months of claims data and break down revenue by payer, not just by percentage of patients. A payer representing 30% of your patient volume but only 15% of your revenue tells you something important about that contract’s real value.
Reimbursement Gap Analysis
For each major payer, compare the in-network fee schedule to your realistic out-of-network collection rate, factoring in denials, appeals, and balance billing limits. This gap, not the headline reimbursement number, is what actually determines which side wins financially.
Run this specialty by specialty if your practice has multiple provider types. A multispecialty group often finds that primary care providers should be in network with a payer while a surgical subspecialty in the same group does better staying out.
Network Adequacy and Referral Flow
In-network status also affects referrals. Specialists who are in network with the major regional payers get more referrals from in-network primary care groups, because those referrals keep the patient’s costs down. Staying out of network can quietly cut off a referral pipeline that never shows up directly in a revenue spreadsheet, but shows up in your new patient numbers a year later.
Common Mistakes Practices Make in This Decision
- Modeling billed charges instead of realistic net collections
- Ignoring denial rates and appeal timelines when estimating out-of-network revenue
- Treating the decision as permanent instead of revisiting it during contract renewal cycles
- Applying one network strategy across every specialty in a multispecialty group
- Overlooking how balance billing limits under the No Surprises Act change historical out-of-network assumptions
- Skipping a formal fee schedule analysis before signing or terminating any payer agreement
Each of these mistakes tends to compound. A practice that models billed charges instead of net collections will overestimate out-of-network revenue, then get blindsided when actual payments come in lower and slower than expected.
How Medwave Approaches This Decision With Clients

We build the model before we make a recommendation. That means pulling real claims data, mapping payer mix by specialty and provider, and running a side-by-side comparison of in-network fee schedules against realistic out-of-network collections, denials included.
For multispecialty groups, we run this at the specialty level, not just the practice level, because the right answer for one provider type is often wrong for another in the same building.
From there, we revisit the model every renewal cycle, not just at signing. Payer terms shift, and so should your strategy.
In-Network vs. Out-of-Network Contracting FAQ
Is Out-of-network billing still profitable after the No Surprises Act?
It can be, but the margin has narrowed for many specialties, especially emergency medicine, anesthesiology, and radiology. Non-emergency out-of-network billing outside of covered facility settings still has more flexibility, but every model should be rebuilt using current rules rather than older assumptions.
Should a multispecialty practice pick one network strategy for the whole group?
No. The right strategy usually varies by specialty and even by individual payer. Primary care providers in a group often benefit from full in-network participation, while a surgical subspecialty in the same practice may do better with a mixed or selective approach.
How often should a practice revisit its in-network vs. out-of-network status?
At minimum, once a year, and always before a contract renewal or termination deadline. Payer fee schedules, patient volume, and regulatory rules all shift, and a decision that made sense three years ago may no longer hold up.
What data do I need before running this analysis myself?
Twelve months of claims data broken out by payer and by provider, your current fee schedules for each in-network payer, and your actual collection rates (not billed charges) for any out-of-network claims from the same period.
Does patient volume matter more than reimbursement rate?
For high-frequency specialties, yes, volume usually wins because losing in-network status can shrink your patient base faster than a higher per-visit rate can offset. For low-volume, high-cost specialties, the reimbursement rate per encounter often matters more than raw patient count.
What is the difference between in-network and out-of-network billing?
In-network billing follows a signed contract with fixed reimbursement rates agreed upon in advance. Out-of-network billing has no such agreement, so reimbursement varies by payer and plan, and patients generally face higher costs.
Can a provider be in-network with some plans and out-of-network with others from the same insurer?
Yes. Many payers offer multiple product lines, such as HMO, PPO, and Medicare Advantage plans, and a provider can be contracted with some products but not others under the same insurance company.
Do out-of-network claims take longer to get paid?
Generally yes. Out-of-network claims often require more documentation, face higher scrutiny, and go through longer review and appeal cycles compared to in-network claims processed under an existing contract.
Is it better to negotiate a new in-network rate or stay out of network?
It depends on your specialty and payer mix. Practices with strong negotiating leverage, such as those with a limited number of competitors in their specialty and region, may secure better in-network rates than the industry standard, which can outperform staying out of network.
Summary: Payer Contracting In-Network vs. Out-of-Network
 Deciding between in-network and out-of-network contracting isn’t a single choice you make once and forget. It’s an ongoing financial model, and the right answer changes by specialty, by payer, and by year. Primary care groups typically need in-network status to protect patient volume, while some procedure-heavy or elective specialties have more room to negotiate a mixed approach. Federal balance billing rules have narrowed the old out-of-network upside for several specialties, so any analysis built on outdated assumptions needs a refresh.
Medwave works with practices across billing, credentialing, and payer contracting to build these models with real claims data, not guesswork, so you know which path actually pays before you sign or terminate a single agreement.

Co-Founder and COO of Medwave, bringing more than 30 years of hands-on experience in healthcare revenue cycle management, payer contracting, and medical credentialing.