

The credentialing committee process is the last checkpoint between a provider’s application and the day that provider can treat patients at your facility. When the committee runs well, verified practitioners start on schedule and revenue follows. When it stalls, files sit between meetings, providers wait weeks for an answer, and every day of delay is a day nobody can bill for their work.
This guide covers what the committee reviews, how to set one up, how to run each meeting cycle, and where technology saves the most time.
Key Takeaways
- The committee’s job is to decide, not to collect paperwork. Files should arrive complete, verified, and with red flags already marked.
- Clear roles, term limits, and a written conflict-of-interest policy keep decisions consistent and defensible.
- Temporary privileges and focused professional practice evaluation (FPPE) need their own written procedures, with time limits that match accreditation standards.
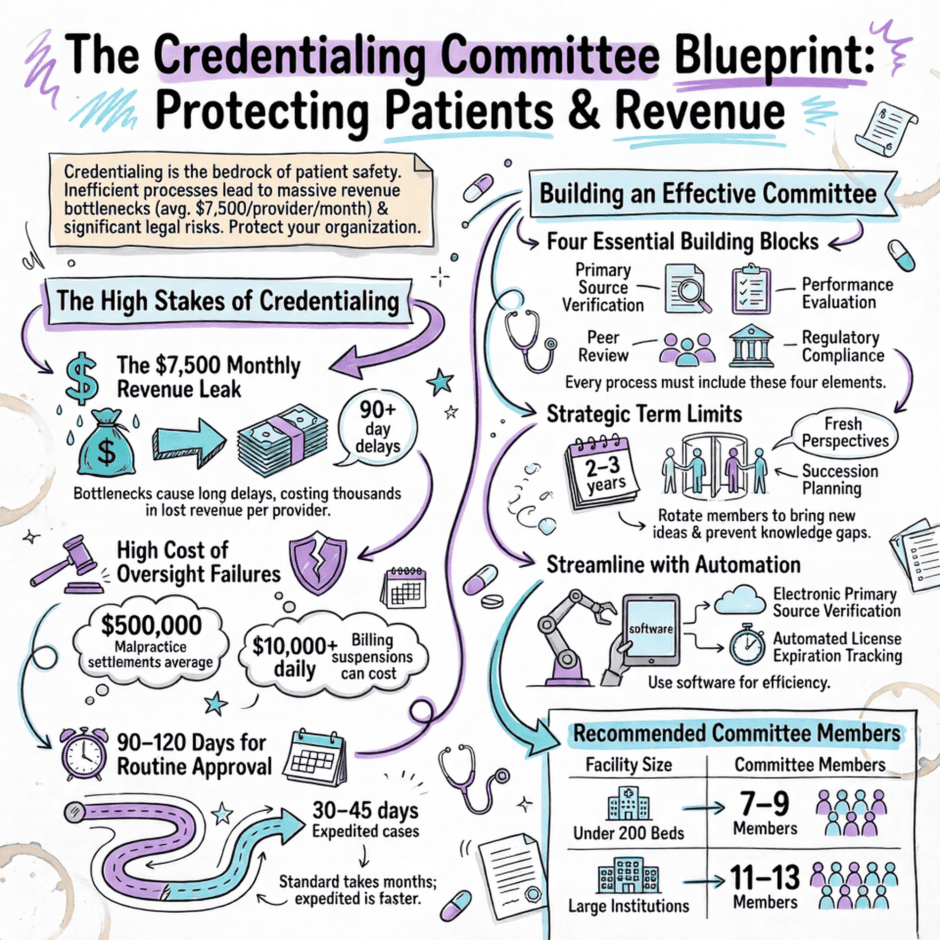
What a Credentialing Committee Does
 A credentialing committee is a group of physicians and administrators with the authority to approve, condition, or deny a practitioner’s application to practice at a facility or join a network. It is the decision point at the end of a longer credentialing process.
Several groups feed into that decision. Medical staff services collects documents and confirms each application is complete. Administrators set policy and make sure credentialing fits the organization’s staffing plans. Quality teams track how the process performs. The practitioners themselves supply the information being verified. When each group knows its role, files move. When responsibilities blur, applications stall in someone’s inbox.
What the Committee Reviews
Every file that reaches the committee should cover four areas.
Primary source verification confirms each credential with the organization that issued it. Staff contact the medical school about the degree, the state board about the license, and the certifying board about board status, rather than accepting copies from the applicant.
Peer review brings in practitioners from the same specialty to assess clinical judgment, outcomes, and professional conduct. A new cardiologist’s file should be read by someone who knows what good cardiology looks like.
Ongoing performance evaluation continues after approval. Outcomes, protocol adherence, and continuing education all feed into the next review cycle, so credentialing doesn’t end on the provider’s first day.
Regulatory compliance ties it together. Medicare, Medicaid, state boards, and accrediting bodies each set requirements, and they change often. NCQA requires recredentialing every three years, for example, so the committee sees each provider again on a fixed schedule.
How to Build the Committee
 There is no single correct size. The committee needs enough members to cover the specialties that regularly apply and few enough that it can reach quorum and decide within one meeting. A small practice group might work with a handful of members, while a multi-hospital system usually needs representation from every major department.
Each member should have a defined role. The chair runs the agenda and moves the group to a decision. The recorder keeps minutes that serve as the official record. Specialty reviewers read files in their own fields and present them.
Term limits of a few years bring in new perspectives and spread the workload, but stagger them so experienced members overlap with new ones. Orientation should walk new members through real cases and your credentialing workflows, not just hand them the bylaws.
Write down a conflict-of-interest policy before you need one. Any member with a personal or financial relationship to an applicant should step out of that review, and the minutes should record the recusal.
Before, During, and After Each Meeting
Most delays happen between meetings, not in them.
Before the meeting, staff should review every file for completeness and request missing items right away. Standard templates for licenses, certifications, and work history make files faster to read and easier to compare. Gaps in employment, malpractice claims, and disciplinary actions should be flagged in advance so the committee isn’t seeing them for the first time.
During the meeting, put urgent and flagged files at the top of the agenda. Present each file in the same format, use the same voting or consensus method for every application, and record the reasoning behind each decision, not just the outcome.
After the meeting, notify providers within days. An approval means the provider can be scheduled and enrolled with payers. A conditional approval needs a written list of what’s missing and a deadline. A denial needs a clear explanation and the appeals process. Conditional approvals with no follow-up owner are a common source of credentialing errors, because the missing item never gets chased.
Legal Protections and Documentation
 Credentialing decisions can be challenged, so the record has to show how each one was made.
Document the rationale for every denial or restriction, including the evidence the committee relied on. Offer a fair hearing to any practitioner whose privileges are denied or limited, and follow the procedure in your bylaws exactly. Keep files confidential, with access limited to the people who need them, because they contain education history, malpractice records, and disciplinary actions.
Assign one person to track regulatory changes and brief the committee. Rules from CMS, state boards, and accrediting bodies shift often enough that waiting for the annual policy review leaves gaps.
Temporary Privileges and FPPE
Some situations can’t wait for the next full review. Disaster response, sudden coverage gaps, and locum tenens providers may all need temporary privileges. The Joint Commission caps temporary privileges for new applicants at 120 days, so the full review has to finish inside that window. Your policy should spell out which verifications are required before temporary privileges are granted and who signs off.
Focused professional practice evaluation (FPPE) is a defined period of closer monitoring. Under Joint Commission standards it applies to practitioners with newly granted privileges, and it begins as soon as temporary privileges start. Committees also use it when a concern comes up about an established provider, such as a complaint or an unexpected outcome. A good FPPE plan names exactly what will be reviewed, such as the next ten procedures or three months of outcomes, and who will review them. At the end, the committee decides whether the provider returns to routine monitoring, needs more training, or faces a change in privileges.
Where Technology Saves Time
 Modern credentialing platforms keep every file in one database, so staff can see each application’s status and missing items at a glance. Many run primary source verification electronically, turning weeks of phone calls into hours.
Online application forms with required fields stop incomplete submissions at the door. Expiration tracking flags licenses and certifications 60 to 90 days out and sends reminders to both the provider and staff. Built-in reporting shows average processing time and error rates without anyone compiling them by hand.
Security matters as much as speed. Choose credentialing software that encrypts data at rest and in transit, limits access by role, and logs who opened each file and when.
Measuring Committee Performance
Track time from submission to decision, broken out by initial applications, recredentialing, and expedited cases. Count how many files come back for corrections, since a high number usually points to unclear forms or instructions.
Ask practitioners what slowed them down. Pull random files each quarter and audit them against your own checklist before an accreditor does. When the same error shows up more than once, treat it as a training gap and fix it at the source.
Credentialing Committee Process FAQ
What is a credentialing committee?
A credentialing committee is a group of physicians, administrators, and other healthcare professionals that reviews verified practitioner files and decides whether to grant privileges or network participation.
How many members should a credentialing committee have?
There is no fixed number. The committee should include enough members to cover the specialties that regularly apply, while staying small enough to reach quorum and make decisions within one meeting.
How often are providers recredentialed?
NCQA requires recredentialing every three years, and most hospitals and health plans follow a similar cycle.
How long can temporary privileges last?
Under Joint Commission standards, temporary privileges for new applicants can be granted for no more than 120 days, so the full credentialing review has to be completed within that period.
What is FPPE and when does a credentialing committee use it?
Focused professional practice evaluation (FPPE) is a defined period of closer monitoring. It applies to practitioners with newly granted privileges and is also used when a concern arises about an established provider’s performance.
What is the difference between credentialing and privileging?
Credentialing verifies a provider’s qualifications. Privileging determines the specific procedures and services that provider is authorized to perform at a given facility.
What happens if a credentialing committee denies an application?
The practitioner receives a written explanation and information about the appeals process, including the right to a fair hearing and the chance to submit additional evidence.
Medwave Keeps Applications Moving to the Committee
 Most of the time a committee spends waiting comes from files that weren’t ready. Missing verifications, expired documents, and unexplained gaps in work history all push decisions to the next meeting. Some files take extra work no matter what, and our credentialing case studies show how our specialists handle difficult provider histories.
Medwave handles credentialing alongside medical billing and payer contracting, with an 85-day average credentialing turnaround. We assemble and verify provider files, track every expiration date, and manage payer enrollment once the committee approves, so a provider’s first day of work is also the first day you can bill for it.
Tell us how many providers you’re onboarding this year, and we’ll show you where the credentialing timeline can tighten.

Co-Founder and COO of Medwave, bringing more than 25 years of hands-on experience in healthcare revenue cycle management, payer contracting, and medical credentialing.