

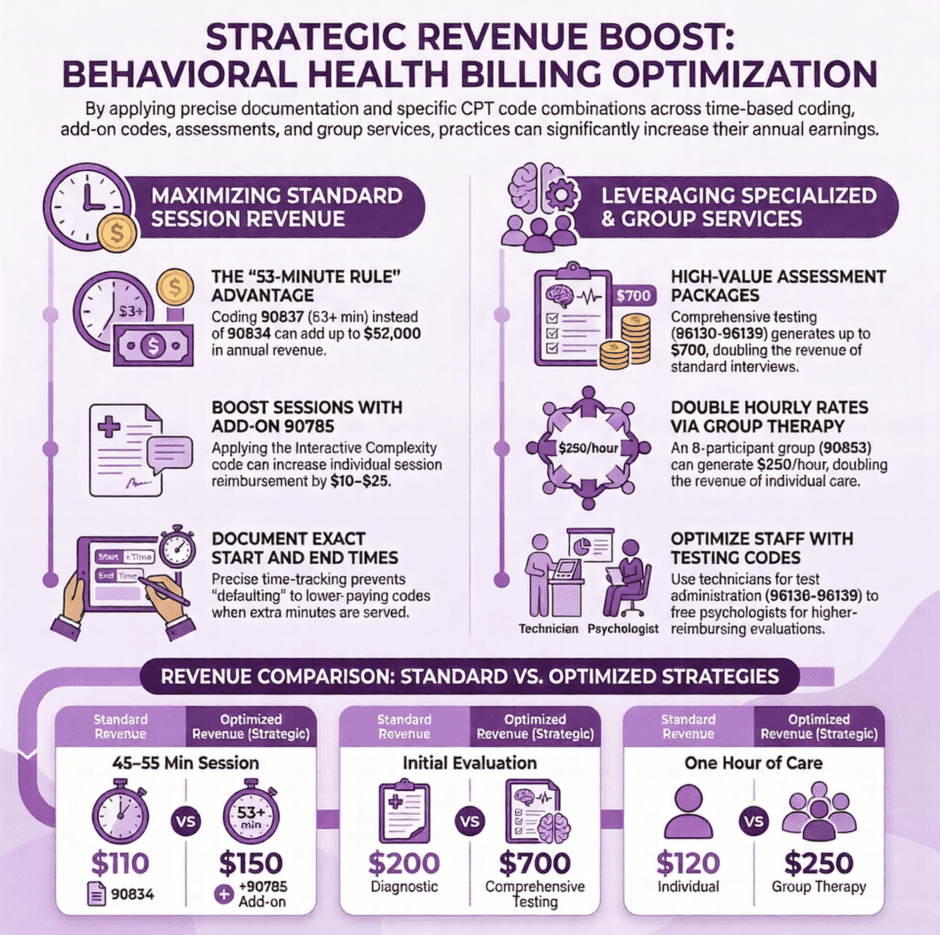
One minute separates two of the most-billed behavioral health CPT codes, and that minute changes what a therapy session pays. A 52-minute session is 90834. At 53 minutes it becomes 90837, provided the note shows the clock.
Reimbursement in mental health rarely hinges on exotic codes. It comes down to time thresholds, add-ons that go unbilled, testing units counted short and Medicare rules that pay one clinician differently from the next. This guide covers the decisions that move revenue for behavioral health practices, from psychotherapy timing to telehealth and integrated care.
Key Takeaways
- Psychotherapy codes are set by documented face-to-face time, with 90837 starting at 53 minutes. Start and stop times in the note are what protect the higher code.
- Interactive complexity (90785) and the psychotherapy add-ons with E/M (90833, 90836, 90838) are frequently missed on mental health claims.
- Medicare pays clinical social workers, marriage and family therapists and mental health counselors 75% of the clinical psychologist fee schedule amount.
- Medicare’s in-person visit requirement for tele-mental health is delayed through December 31, 2027.
- Integrated care codes such as 99484, G0323 and 99492–99494 pay for work between sessions that many practices already do without billing.
Psychotherapy Time Thresholds That Set the Payment
Individual psychotherapy is billed by time, and the boundaries are fixed in CPT. Getting the code right is mostly a documentation habit rather than a coding judgment.
The 90832, 90834 and 90837 Time Ranges

90832 covers 16 to 37 minutes of psychotherapy with the patient or family. 90834 covers 38 to 52 minutes, and 90837 applies at 53 minutes or longer. Sessions under 16 minutes are not reportable as psychotherapy. A practice that schedules 50-minute hours and bills every session as 90834 is coding correctly, but a clinician who routinely runs to 55 minutes and still bills 90834 is leaving the difference on the table.
Documenting Time That Holds Up on Audit
Record the start and stop times in every note rather than a rounded total. A note reading “Session 2:00 PM to 2:54 PM, 54 minutes” supports 90837 on its face. Pair the time with what happened in the session and how it ties to the treatment plan, because payers that audit 90837 look for both. Some commercial plans track each clinician’s ratio of 90837 to 90834, so a high ratio needs notes that justify it.
Psychotherapy Add-On Codes With E/M
Psychiatrists and psychiatric nurse practitioners who manage medication and provide therapy in the same visit bill an E/M code plus 90833, 90836 or 90838. The add-on time bands mirror the standalone codes at 16, 38 and 53 minutes. Choose the E/M level by medical decision making, since psychotherapy time cannot also be counted toward E/M time. The note should make the two services distinguishable on its own.
Add-On and Crisis Codes Practices Underbill
The base psychotherapy code is only part of the claim when a session involves extra work or an emergency.
Interactive Complexity With 90785
90785 is added when communication factors make the service harder to deliver. Examples include a caregiver whose emotions interfere with the session, the need to manage conflicting participants, or a sentinel event that requires a report to a third party. It can be reported with diagnostic evaluations (90791, 90792), individual psychotherapy and group psychotherapy (90853). It cannot be billed with crisis codes or with an E/M service alone. Document the specific factor, because a note that only says “complex session” will not support the add-on.
Crisis Psychotherapy With 90839 and 90840
90839 covers the first 30 to 74 minutes of psychotherapy for a patient in crisis. Each additional 30 minutes beyond that is reported with 90840. Crisis codes require an urgent assessment and interventions aimed at reducing distress, so a routine session that turns difficult does not automatically qualify. Medicare allows clinical psychologists, social workers, marriage and family therapists and counselors to bill these codes, including by telehealth.
Family and Group Sessions
Family psychotherapy is coded 90846 without the patient present and 90847 with the patient. Group psychotherapy is 90853, and multiple-family groups use 90849. Group notes need an individual entry for each participant that describes their participation and progress, since one shared group note does not support a claim for each member.
Psychological Testing Units Without Undercounting
Testing pays well, yet claims often report fewer units than the work supports because the codes split one evaluation into several parts.
Evaluation Services
96130 covers the first hour of psychological testing evaluation by a physician or qualified professional, and 96131 covers each additional hour. Evaluation time includes integrating patient data, interpreting results, clinical decision making, the report and feedback to the patient or family. Under CPT time rules a unit is reached once the midpoint is passed, so the first hour of 96130 needs at least 31 minutes.
Administration and Scoring
Test administration by the professional is billed as 96136 for the first 30 minutes and 96137 for each additional 30 minutes. When a technician administers the tests, the codes are 96138 and 96139. A single automated instrument with automated results is 96146. Track evaluation time and administration time separately in the record, since a claim needs both sets of codes to capture a full battery.
A Typical Unit Set
A neuropsychological battery might report 96130 for one unit and 96131 for two units. Add 96136 and 96137 for professional administration, plus 96138 and 96139 units for technician time. Each line needs time documented in the record, and payers that require prior authorization for testing often cap the total hours approved.
Who Bills Medicare and at What Rate
Medicare pays the same psychotherapy code at different rates depending on the clinician’s license, which makes staffing a revenue decision.
Payment by Provider Type
Physicians and clinical psychologists are paid 100% of the fee schedule amount. Nurse practitioners and physician assistants are paid 85% of the physician amount. Clinical social workers, marriage and family therapists and mental health counselors receive 75% of the clinical psychologist amount, and all three must accept assignment. Marriage and family therapists and counselors have been able to enroll in Medicare since January 1, 2024, which opened Medicare panels to many practices for the first time. The CMS Medicare and mental health coverage booklet lists the rates and enrollment rules.
How the Current Fee Schedule Treats Behavioral Health
The current Medicare Physician Fee Schedule raised the conversion factor and applied a 2.5% efficiency cut to work values for most procedures. Time-based services, including behavioral health codes, were exempt from that cut. A separate change lowered practice expense values for services billed in facility settings, so hospital-based behavioral health groups saw less benefit than office-based practices.
Incident-To and Supervision
Behavioral health services provided by auxiliary personnel incident to a physician or other billing practitioner can be furnished under general supervision instead of direct supervision. Social workers, therapists and counselors generally cannot bill their own services incident-to, though they can work as auxiliary personnel under a physician, psychologist, NP, PA, CNS or CNM.
Telehealth Billing for Behavioral Health
Telehealth now carries a large share of therapy volume, and the rules differ by payer more than any other part of the claim. Our article on telehealth billing complexity covers the broader trend.
Medicare’s Permanent Mental Health Telehealth Rules
Medicare covers mental health telehealth permanently, with the patient’s home allowed as the originating site and no geographic restriction. Audio-only services are allowed when the patient cannot use video or does not want to, and those claims carry modifier 93. Use POS 10 when the patient is at home and POS 02 for other locations, and confirm with your MAC whether modifier 95 is also required. For the current year, CMS also added multiple-family group psychotherapy (90849) to the telehealth list.
The In-Person Visit Requirement
Federal law requires an in-person visit within six months before a new tele-mental health patient’s first telehealth service and periodically after that. The Consolidated Appropriations Act, 2026 delayed that requirement through December 31, 2027, as McGuireWoods explains in its summary of the extension. Practices should still build the in-person visit into intake workflows now, since the requirement returns on January 1, 2028 unless Congress acts again.
Commercial and Medicaid Telehealth
Commercial plans and state Medicaid programs set their own place of service and modifier rules, and some pay telehealth at a lower rate than in-person visits. Keep a payer-by-payer list of required modifiers, because a claim with the wrong POS for that plan is often rejected before it reaches adjudication.
Integrated Care Codes Beyond the Therapy Session
Coordination with primary care between visits is billable work when the program is set up to track the minutes.
General Behavioral Health Integration
99484 covers at least 20 minutes per calendar month of clinical staff time directed by a physician or other qualified professional for a patient with a behavioral health condition. Clinical psychologists, social workers, marriage and family therapists and counselors bill general BHI with G0323, also under general supervision. A patient enrolled in BHI and chronic care management needs each program’s time documented separately so no minute is counted twice.
Psychiatric Collaborative Care
The collaborative care model uses 99492 for the first month, 99493 for later months and 99494 for each additional 30 minutes, with G2214 for a shorter 30-minute month. These codes are billed by the treating primary care practitioner and require a behavioral health care manager and a psychiatric consultant working from a shared registry.
Rural Health Clinics and FQHCs
G0511 stopped being payable on October 1, 2025, so RHCs and FQHCs now bill care management with the individual codes. Collaborative care codes 99492–99494 became billable for RHCs from January 1, 2026, according to the NARHC summary of the final rules. Clinics using advanced primary care management can add optional behavioral health integration add-ons instead.
Digital Mental Health Treatment
G0552 covers supplying an FDA-cleared digital mental health treatment device and onboarding the patient, and G0553 and G0554 cover monthly treatment management. The device has to fall within the FDA classifications CMS lists, and the billing practitioner must order it and carry its cost. CMS has not yet extended these codes to ADHD devices.
Commercial and Medicaid Payer Rules
Outside Medicare, the same CPT code can come with authorization limits or a different code set entirely.
Authorizations and Visit Limits
Many plans require prior authorization for psychological testing and intensive outpatient programs, and some authorize therapy in blocks of visits. Track the authorized count and end date against scheduled sessions so a claim is never filed after the authorization runs out.
Medicaid H Codes and State Rules
State Medicaid programs often pay community behavioral health services under HCPCS H codes rather than CPT. Our reference guide to behavioral health billing codes lists H0004, H0031, H2019 and the other common H codes. Unit definitions and modifiers vary by state, so the state’s provider manual is the source of truth.
Rejections Versus Denials
Many behavioral health claims never reach a payment decision because of front-end errors such as an inactive subscriber ID or a missing taxonomy code. Knowing the difference between a claim denial and a rejection tells your team whether to correct and resubmit or to appeal.
Auditing Your Own Claims Before a Payer Does
A quarterly self-audit catches undercoding and compliance risk at the same time.
What to Sample
Pull 20 claims per clinician and compare the billed code with the documented time. Check whether add-ons were supported where billed and missed where the note supported them. Review testing claims for units that match the documented minutes.
Reading the Results
Compare each clinician’s 90837 ratio with the group average, and look at whether Medicare patients are scheduled with the license type that matches their complexity. Errors that repeat across a clinician’s claims usually point to a template problem rather than a training one.
Fixing the Workflow
Most fixes belong in the EHR. Add required time fields to psychotherapy templates and a prompt for interactive complexity factors. Make sure your system’s connection to the clearinghouse passes modifiers and place of service codes through without manual edits.
Psychotherapy Reimbursement FAQ
How many minutes are required to bill CPT 90837?
CPT 90837 requires at least 53 minutes of psychotherapy with the patient or family member. Sessions from 38 to 52 minutes are billed as 90834, and sessions from 16 to 37 minutes as 90832.
Can 90785 be billed with every psychotherapy session?
No. Interactive complexity is billed only when a specific communication factor made the service harder to deliver, and the note must describe that factor. It cannot be reported with crisis psychotherapy codes 90839 and 90840.
What percentage of the fee schedule does Medicare pay LCSWs, LMFTs and counselors?
Medicare pays clinical social workers, marriage and family therapists and mental health counselors 75% of the clinical psychologist fee schedule amount. Nurse practitioners and physician assistants receive 85% of the physician amount.
Is an in-person visit required before Medicare tele-mental health services?
The requirement exists in law but has been delayed through December 31, 2027. Unless Congress extends it again, new patients will need an in-person visit within six months before their first tele-mental health service starting January 1, 2028.
What is the difference between 99484 and G0323?
Both cover general behavioral health integration of at least 20 minutes per month. 99484 is billed by physicians and other practitioners who direct clinical staff, while G0323 is billed by clinical psychologists, social workers, marriage and family therapists and mental health counselors.
Which codes are used for psychotherapy during a medication management visit?
Bill the E/M code for the medical portion and add 90833, 90836 or 90838 for the psychotherapy time. The E/M level is chosen by medical decision making, and the psychotherapy minutes cannot be counted toward the E/M service.
How is psychological testing time billed?
Evaluation work is billed with 96130 for the first hour and 96131 for each additional hour. Administration is billed in 30-minute units, with 96136 and 96137 when the professional administers tests and 96138 and 96139 when a technician does.
Where Medwave Fits in a Behavioral Health Revenue Cycle
 Therapy practices tend to lose revenue in small increments. A session coded one band low costs little on its own. Repeat it across a full caseload for a year, add a counselor who never got enrolled with Medicare, and the gap becomes real money.
Medwave has supported 15,000+ providers, and our medical billing team holds a 98% clean claim rate. For behavioral health groups we review note templates for time capture and keep authorizations from lapsing. Our credentialing team enrolls new clinicians with commercial plans and Medicare in an average of 85 days. If your notes support more than your claims are paying, send us a message below.
Disclaimer: This article is provided for informational purposes only and does not constitute legal, billing or financial advice. CPT codes, Medicare rules and payer policies change, and providers should verify current requirements with each payer before applying any coding approach. CPT® is a registered trademark of the American Medical Association.

Co-Founder and COO of Medwave, bringing more than 25 years of hands-on experience in healthcare revenue cycle management, payer contracting, and medical credentialing.