

- Where Should Payer Payments Go When I Use a Billing Company?
- Is It Legal for a Billing Company to Charge a Percentage of Collections?
- What Should a Billing Company’s BAA Say About a Data Breach?
- Does a BAA Make the Billing Company Liable Instead of Me?
- Do I Need a Business Associate Agreement with a Medical Billing Company?
- What is Fee Schedule Drift?
- How Do I Update Credentialing after a Name Change?
- Can I Credential a Locum Tenens Provider?
- What Causes Insurance Credentialing Delays?
- How Do I Credential a New Provider Faster?
- What is a Denial Rate?
- Why Do Modifier Errors Happen?
- What are the Most Common Modifier Errors?
- What is a Modifier Error?
- What Ongoing Monitoring Should Providers Do for Contracted Payers?
- How Do Rate Negotiations Work for Ancillary Services?
- What is the Difference Between Contracted Rates and Billed Charges?
- How Do Practice Mergers or Acquisitions Affect Existing Payer Contracts?
- What are Common Rate Negotiation Timelines and Deadlines?
- How Do Quality Metrics in Payer Contracts Affect Reimbursement?
- What Should Providers Know about Fee Schedule Updates?
- How Do Outlier Payments Work in Bundled Payment Arrangements?
- What Leverage Do Specialty Providers Have in Contract Negotiations?
- How Do Payer Contracts Handle Telehealth Services?
- What is Primary Source Verification in Credentialing?
- How Do You Maintain Credentials Across Multiple States?
- What Happens if a Provider’s License or Certification Expires During Active Credentialing?
- How Do Hospital Privileges Relate to Insurance Credentialing?
- What Credentialing Challenges Do New Medical Practices Face?
- How Do You Handle Patients Who Cannot Pay Their Medical Bills?
- What is a Clearinghouse and How Does it Help with Medical Billing?
- How Do You Handle Coordination of Benefits When Patients Have Multiple Insurance Policies?
- What Role Does the Explanation of Benefits (EOB) Play in Medical Billing?
- How Does Bundling Affect Medical Billing Reimbursement?
- What is the Appeals Process for Denied Medical Claims?
- How Do you Determine the Right CPT Code for a Service?
- What Documentation do Payers Require to Support Medical Billing Claims?
- How Does Medical Billing Work for Practices with Multiple Locations?
- What are the Most Common Medical Billing Errors that Lead to Claim Denials?
- What is Privileging?
- What is a Credentialing Committee?
- How Do I Handle Out-of-Network Billing Situations?
- Can Medwave Help If I’m Joining an Existing Practice or Leaving One?
- What is the Difference Between a Claim Denial and a Claim Rejection?
- How Do Value-Based Care Contracts Differ from Traditional Fee-for-Service Contracts?
- What is a Modifier in Medical Billing and When Should I Use One?
- What Should I Do If an Insurance Company is Consistently Underpaying Claims?
- Do I Need Separate Malpractice Insurance for Telehealth Services?
- What is Medical Necessity and Why Do Claims Get Denied for Lack of It?
- How Long Do Insurance Companies Have to Pay Claims?
- What Clean Claim Rate Should My Practice Aim For?
- What is the National Provider Identifier (NPI) and Do I Need One?
- How Does Moving to a New State Affect My Credentialing and Payer Contracts?
- What is the Difference Between Credentialing and Privileging?
- Can I Bill Insurance Companies While My Credentialing is in Progress?
- What does a DataSpring CAQH application error actually cost in lost revenue?
- What Happens if My Credentialing Application is Denied?
- What Common Mistakes Should I Avoid During the Credentialing Process?
- What is Recredentialing and How Often Does it Occur?
- What Documents and Information Do I Need to Prepare for Credentialing?
- What Happens if I Want to Terminate a Payer Contract or if a Payer Terminates Me?
- Can I Negotiate Better Rates with Insurance Companies, and What Leverage Do I Have?
- What Key Terms Should I Focus on When Negotiating Payer Contracts?
- How Long Does the Typical Payer Contracting Process Take?
- What is Payer Contracting and Why is it Important for Healthcare Providers?
- How Important is Medical Credentialing to a Healthcare Provider?
- Do You Support Healthcare Providers that Perform Telehealth / Telemedicine?
- What is Medical Billing?
- What is Medical Credentialing?
- What Type(s) of Family Practice Medical Billing Services Do We Offer?
- What Insurers Have We Worked with in the Past?
- What are Our Rates?
- What Types of Medical Practices do We Serve?
- Do You Support Cannabis Medicine with their Billing Requirements?
- Do You Support Genetic Testing Labs with their Billing Needs?
- Do You Fix Denied Medical Claims?
- Is A/R Recovery Part of Your Services?
- Which Regions do We Serve w/ Billing & Credentialing Service?
- What’s Your Medical Credentialing On-Board Protocol?
- Do You Partner with 3rd Party Medical Groups?
- Do You Provide Billing and / or Credentialing to Laboratories?
Where Should Payer Payments Go When I Use a Billing Company?
Ask for payer deposits to go to a bank account in your practice’s name that you control. The Medicare and Medicaid rules restrict payment to billing agents, and a practice-controlled account keeps the billing company out of the payment path. Your agreement should also say whether the fee is calculated on collections or on billed charges. Our breakdown of whether billing companies are worth it covers which dollars the fee applies to and what leaving costs.
Is It Legal for a Billing Company to Charge a Percentage of Collections?
Often, yes, but it depends on who receives the payments and which payers are involved. Medicare allows payment to a billing agent only when the agent’s pay is not related in any way to the dollars billed or collected, under 42 CFR 424.73, and Medicaid has a parallel rule for business agents at 42 CFR 447.10. Some states add their own limits, so have an attorney review the fee terms. Our guide to billing service costs compares percentage, per-claim, and flat monthly pricing.
What Should a Billing Company’s BAA Say About a Data Breach?
It should require the billing company to report security incidents, including breaches of unsecured patient information, back to you. Ask for a deadline measured in days so you are not waiting on the vendor’s own timeline. Also ask who their subcontractors are, since a vendor that shares patient information with a subcontractor needs a BAA with that subcontractor first.
Does a BAA Make the Billing Company Liable Instead of Me?
No. Business associates carry direct liability for parts of the HIPAA Rules, and you keep your own duties. If you learn of a pattern of activity amounting to a material breach by your billing company, you have to take reasonable steps to cure it and, if that fails, end the agreement where feasible.
Do I Need a Business Associate Agreement with a Medical Billing Company?
Yes. HIPAA allows a provider to disclose patient information to a business associate only after getting satisfactory assurances in a written agreement, and HHS lists billing and claims processing among business associate functions. Get the agreement signed before the billing company receives any patient information. HHS publishes sample BAA provisions you can compare against a vendor’s draft.
What is Fee Schedule Drift?
Fee schedule drift is the gradual, often unnoticed change in payer reimbursement rates over time. It happens through routine CMS updates, RVU adjustments, quarterly patches, and payer-specific repricing that most practices never actively track. Each change on its own looks small, but stacked over months or years, drift can quietly shift what a practice actually collects for the same codes it billed a year ago.
The risk is that drift rarely announces itself. A claim can process cleanly and still pay less than expected, so there’s no denial or rejection to flag the problem. Practices that don’t audit claims against current fee schedules on a regular basis often discover drift only after months of underpayment have already added up, which is why routine rate checks matter as much as clean claim submission.
How Do I Update Credentialing after a Name Change?
Notify each payer as soon as the change happens. Update CAQH, licenses, and tax records with matching information. Keep legal proof of the name change on file.
Can I Credential a Locum Tenens Provider?
Yes, many payers will credential locum tenens providers. Requirements vary by payer and time period of service. Always confirm the payer’s rules before scheduling.
What Causes Insurance Credentialing Delays?
Delays usually come from missing information, expired documents, or slow payer review. Work history gaps and primary source verification can also slow things down. Clean submissions reduce most of the wait.
How Do I Credential a New Provider Faster?
Start early and submit a complete application the first time. Keep CAQH, licenses, and supporting documents current. Follow up with each payer regularly.
What is a Denial Rate?
Denial rate in medical billing is the percentage of submitted claims that a payer denies. To calculate it, divide the number of denied claims by the total number of claims submitted in the same period, then multiply by 100. A practice that submits 1,000 claims in a month and has 50 denied has a denial rate of 5 percent.
Two versions of the number are worth tracking. The initial denial rate counts every claim denied on first submission, including those later paid on appeal. The final denial rate, sometimes called the write-off rate, counts only the claims that are never paid. A high initial rate with a low final rate points to costly rework. A high final rate means revenue is being lost.
Many billing teams aim to keep the initial denial rate under 5 percent. Practices often run higher because of coding errors, missing documentation, eligibility problems, or absent prior authorization. The overall rate hides most of the story, so break it down by payer, CPT code, provider, and denial reason code. A single payer or a single code often accounts for a large share of denials, and that is where fixing the process pays off first.
Denial rate pairs naturally with clean claim rate, since clean claims are the ones least likely to be denied. The most common causes and fixes are listed in Common Denial Codes in Billing + How to Fix Them, and denial management covers how to work the claims that are already denied.
Why Do Modifier Errors Happen?
Payer rules around modifiers are not uniform. What one insurance company accepts, another may reject. Without up-to-date knowledge of each payer’s specific guidelines, it is easy for billing staff to apply modifiers inconsistently.
What are the Most Common Modifier Errors?
The ones that come up most often include leaving off a modifier entirely, using a modifier that does not match the procedure or payer’s rules, stacking too many modifiers on a single code, and using informational modifiers in the wrong position when payment modifiers need to come first.
What is a Modifier Error?
A modifier error happens when the wrong modifier is used, a required modifier is left off, or a modifier is attached to a code it does not belong with. These mistakes are among the most common billing errors practices face, and they can lead to claim denials, reduced reimbursements, or even audits.
What Ongoing Monitoring Should Providers Do for Contracted Payers?
Active contract management requires regular monitoring beyond initial negotiation. Track actual payment rates against contracted rates to identify underpayments, monitor denial rates by payer to spot problematic patterns, review days in accounts receivable by payer to identify slow payers, and track volume trends to see if patient loads are shifting. Document any payer practices that violate contract terms, such as missed payment deadlines or improper bundling. This ongoing monitoring identifies issues requiring action and builds documentation supporting future negotiations or contract termination if necessary.
How Do Rate Negotiations Work for Ancillary Services?
Ancillary services like laboratory, radiology, or physical therapy often face different negotiation dynamics than professional services. Payers may have less detailed rate schedules for certain ancillary services, creating negotiation opportunities. Ancillary services with significant equipment costs or technical components may have more rate variation between payers. Demonstrating lower per-test costs, faster turnaround times, or better quality metrics strengthens negotiating position. Some ancillary services face downward rate pressure from national reference labs or imaging chains, requiring strong local value propositions.
What is the Difference Between Contracted Rates and Billed Charges?
Contracted rates are the amounts a payer has agreed to pay for each service under a network contract. Billed charges are the amounts a provider lists on a claim, drawn from the practice’s own fee schedule or chargemaster. For in-network services, the payer pays according to the contracted rate, also called the allowed amount, and the provider writes off the difference as a contractual adjustment.
Here is a worked example. A practice bills $300 for a service and the contracted rate is $180, so the practice writes off the $120 difference. If the patient owes a $30 copay, the payer pays $150 and the practice collects $180 in total. The patient’s cost sharing is calculated on the $180 allowed amount and never on the $300 charge.
Billed charges still matter in a few situations. Out-of-network payments are sometimes set as a percentage of billed charges or of usual and customary rates, which makes the charge amount a direct input to payment. Charges should sit at or above the highest contracted rate so the write-off never turns into a shortfall.
Review your chargemaster on a regular schedule and compare each payer’s contracted rates with what you are being paid. The explanation of benefits shows the billed amount, the allowed amount, and the adjustment on every claim, which makes underpayments easier to spot. When rates fall behind, payer contracting is where they get renegotiated.
How Do Practice Mergers or Acquisitions Affect Existing Payer Contracts?
Practice changes trigger contract reviews and potential renegotiations. Payers typically have change-of-control clauses allowing them to review or terminate contracts when practices merge or are acquired. Tax ID number changes require new contract execution in most cases. The acquiring entity may need to credential all providers under new arrangements. These transitions should be planned carefully with adequate lead time, as there may be gaps in network participation during the transition. Negotiating how mergers affect contracts before completing the business transaction prevents unwelcome surprises.
What are Common Rate Negotiation Timelines and Deadlines?
Rate negotiations typically align with contract renewal periods. Payers usually send renewal notices 90-180 days before contract expiration, opening the negotiation window. Some contracts allow for annual rate discussions even without full contract renewal. Request rate increases at least 120 days before renewal to allow time for review and back-and-forth discussion. If negotiations aren’t progressing and you’re considering termination, most contracts require 90-180 days advance notice. Missing these deadlines often means accepting existing rates for another contract term.
How Do Quality Metrics in Payer Contracts Affect Reimbursement?
Quality metrics increasingly tie to payment through various mechanisms. Pay-for-performance programs provide bonuses for achieving quality targets or penalties for poor performance. Value-based contracts may withhold a percentage of payments (typically 2-10%) that’s earned back by meeting quality benchmarks. Quality metrics commonly include clinical measures like diabetic control or preventive care rates, patient satisfaction scores, efficiency measures like generic prescribing rates, and utilization metrics like readmission rates. Understanding which metrics affect your payment and focusing improvement efforts on those measures maximizes financial performance.
What Should Providers Know about Fee Schedule Updates?
Payers update fee schedules periodically, sometimes annually or when Medicare releases rate changes. Contracts should specify how and when payers notify providers of fee schedule changes. Some changes are automatic based on Medicare updates, while others require mutual agreement. Providers should review fee schedule updates carefully to identify significant rate reductions that might warrant renegotiation or contract termination. Understanding how your contract handles fee schedule updates and whether you can contest changes protects your practice from surprise rate cuts.
How Do Outlier Payments Work in Bundled Payment Arrangements?
Outlier payments provide additional reimbursement when costs significantly exceed the bundled payment amount, protecting providers from excessive financial risk. Outlier thresholds define how far costs must exceed the bundle before additional payment triggers, typically 2-3 times the bundled amount. When costs surpass this threshold, providers receive a percentage of costs above the threshold. Outlier provisions are important in bundled payment arrangements because they limit downside risk from unusually expensive cases while maintaining incentives for efficiency in typical cases.
What Leverage Do Specialty Providers Have in Contract Negotiations?
Specialty providers often have significant negotiating leverage, particularly if they offer unique services or subspecialty expertise in their market. Limited specialist availability in an area strengthens negotiating position, as payers need adequate specialty coverage for network adequacy. Quality metrics, patient satisfaction scores, and efficient care delivery provide additional leverage. Specialists with hospital-based procedures may have more leverage than office-based specialties. Building data demonstrating your value to the payer’s network strengthens negotiating position for rate improvements.
How Do Payer Contracts Handle Telehealth Services?
Telehealth contract provisions vary widely by payer. Some contracts specifically address telehealth reimbursement rates, which may match in-person rates or be discounted. Contracts may limit which services can be provided via telehealth, specify acceptable technology platforms, and define geographic restrictions for where patients must be located. Some require specific telehealth-related modifiers on claims. As telehealth expands, reviewing and negotiating telehealth terms in payer contracts becomes increasingly important for practices offering virtual services.
What is Primary Source Verification in Credentialing?
Primary source verification is the process of confirming a provider’s credentials directly with the organization that issued them, instead of relying on copies, a CV, or the provider’s own statements. It is a core requirement of payer and hospital credentialing and a main reason the process takes weeks.
What Gets Verified
- State medical license, checked with the issuing state board
- Education and residency or fellowship training, confirmed with the school or program
- Board certification, confirmed with the specialty board
- DEA registration, checked with the DEA
- Work history and any gaps, confirmed with prior employers
- Malpractice claims history and National Practitioner Data Bank results
- Sanction and exclusion lists, such as the OIG exclusion list
Each check depends on someone else’s response time. Boards and schools answer on their own schedules, and prior employers can take weeks to return a work history. Providers cannot speed those responses up, but they can avoid delays by listing exact dates, using names that match across every document, and replying quickly when a credentialing specialist asks for a missing item. Verification software shortens some checks, a trend covered in How Technology is Fixing Primary Source Verification. For the full timeline picture, see how long medical credentialing takes.
How Do You Maintain Credentials Across Multiple States?
Multi-state credentialing requires systematic tracking of state-specific requirements. Each state has its own medical board, licensing requirements, and renewal timelines. Providers need separate licenses for each state where they practice, including telehealth services. Malpractice insurance must cover all practice states. CAQH profiles should list all state licenses. Some states participate in interstate medical licensure compacts that streamline multi-state licensing, but credentialing still requires state-by-state applications with most payers.
What Happens if a Provider’s License or Certification Expires During Active Credentialing?
Expired licenses or certifications create immediate credentialing problems. Most contracts require continuous maintenance of all credentials as a condition of network participation. If a license expires, providers must immediately notify all payers and facilities where they’re credentialed. The provider may be suspended from seeing insured patients until licensure is renewed and verified. Claims submitted during periods of expired licensure may be denied, and retroactive billing might not be allowed even after renewal. Setting up license renewal reminders well in advance prevents these disruptions.
How Do Hospital Privileges Relate to Insurance Credentialing?
Hospital privileges and insurance credentialing are separate but related processes. Hospital credentialing grants permission to admit and treat patients at that facility, while insurance credentialing allows billing that insurer for services. Many insurance companies require active hospital privileges as part of their credentialing criteria, viewing hospital affiliation as validation of clinical competence. Loss of hospital privileges can trigger notification requirements to insurance companies and may jeopardize insurance panel participation depending on contract terms.
What Credentialing Challenges Do New Medical Practices Face?
New practices encounter several hurdles including lack of practice history that payers typically review, no prior claim data to demonstrate volume or quality, longer approval timelines as new entities, potential delays in obtaining all necessary licenses and registrations, and difficulty demonstrating patient base without existing patient volumes. New providers should start credentialing applications 6-9 months before intended practice start date, maintain complete documentation, and consider interim solutions like locum tenens arrangements while awaiting full credentialing approval.
How Do You Handle Patients Who Cannot Pay Their Medical Bills?
Managing patient collections requires balancing financial needs with patient relationships. Options include offering payment plans with manageable monthly installments, providing financial assistance programs for qualifying patients, negotiating reduced lump-sum settlements, or referring accounts to collection agencies as a last resort. Clear communication about financial responsibility before services, transparency about costs, and compassionate but persistent follow-up helps maximize collections while maintaining patient satisfaction. Some practices offer prompt-payment discounts for full payment at time of service.
What is a Clearinghouse and How Does it Help with Medical Billing?
A clearinghouse acts as an intermediary between providers and payers, electronically transmitting claims and returning responses. Clearinghouses scrub claims for errors before submission, checking for common mistakes that would cause rejections. They translate claims into formats required by different payers, provide real-time eligibility verification, and return electronic remittance advice (ERA) showing payment details. Using a clearinghouse typically reduces rejection rates and speeds up the billing process compared to submitting paper claims directly to payers.
How Do You Handle Coordination of Benefits When Patients Have Multiple Insurance Policies?
Coordination of benefits (COB) determines which insurance pays first (primary) and which pays second (secondary). The birthday rule typically determines order for dependent children, with the parent whose birthday falls earlier in the calendar year being primary. For spouses, each person’s own insurance is usually primary for themselves. Claims must be submitted to the primary payer first, then the secondary payer receives the claim with the primary payer’s EOB. Improper COB filing causes delays and denials, so verifying correct payer order before billing is essential.
What Role Does the Explanation of Benefits (EOB) Play in Medical Billing?
EOBs provide detailed information about how a claim was processed, including allowed amounts, patient responsibility, denial reasons, and adjustment codes. Reviewing EOBs carefully helps identify underpayments, incorrect patient balances, and patterns in denials. EOBs contain important information for patient billing, showing what insurance paid and what the patient owes. They also provide appeal rights information and contact details for questions. Systematic EOB review is essential for effective revenue cycle management and identifying issues requiring follow-up.
How Does Bundling Affect Medical Billing Reimbursement?
Bundling occurs when payers group multiple related services into a single payment rather than paying for each separately. The Correct Coding Initiative (CCI) defines which codes bundle and under what circumstances. Some bundled services can be billed separately with appropriate modifiers like -59 or -25 when documentation supports distinct services. Bundling significantly impacts reimbursement because practices receive one payment instead of multiple, often resulting in lower total reimbursement than if services were paid separately.
What is the Appeals Process for Denied Medical Claims?
The appeals process typically has multiple levels. First-level appeals are often informal reviews where you submit additional documentation or clarification to the payer. If denied again, second-level appeals may involve peer-to-peer review with a medical director. Third-level appeals might go to an external review organization. Each level has specific deadlines, usually 30-180 days depending on the payer and appeal stage. Appeals should include clear explanations of why the service was medically necessary, relevant medical records, applicable clinical guidelines, and references to policy language supporting coverage.
How Do you Determine the Right CPT Code for a Service?
CPT code selection requires matching the service provided to the most specific code description available. Review the complete code description, including any parenthetical notes and code-specific guidelines. Consider the anatomical location, approach, and extent of the service. Check for bundling rules and mutually exclusive edits that might require modifiers. When multiple codes could apply, select the one that most accurately describes the work performed. Regular training on coding updates and specialty-specific coding guidelines helps ensure accuracy.
What Documentation do Payers Require to Support Medical Billing Claims?
Required documentation varies by service type and payer, but generally includes detailed provider notes describing the service rendered, diagnosis codes supported by clinical findings, medical necessity justification, and any applicable test results or imaging reports. For procedures, operative reports and procedural notes are essential. Time-based services require specific time documentation. Prior authorization approvals must be documented and referenced on claims. Payers may request additional records during audits, so maintaining thorough documentation for all patient encounters is critical for defending billed services.
How Does Medical Billing Work for Practices with Multiple Locations?
Multi-location billing requires careful attention to location-specific details. Each office location typically has its own place of service code, may have different payer contracts with varying rates, and might serve different patient populations. Claims must be submitted with the correct location information to ensure proper reimbursement. Some practices use a centralized billing office that handles all locations, while others maintain separate billing staff at each site. Reporting should track performance by individual location while also providing consolidated practice-wide metrics.
What are the Most Common Medical Billing Errors that Lead to Claim Denials?
The most frequent billing errors include incorrect patient demographics like misspelled names or wrong dates of birth, invalid insurance ID numbers, missing or incorrect provider information, coding errors such as using outdated CPT codes or mismatched diagnosis codes, and lack of required authorizations. Duplicate claim submissions also trigger denials, as do services billed beyond the timely filing deadline. Many denials stem from simple data entry mistakes that could be caught with proper quality control checks before submission.
What is Privileging?
Privileging is the process of granting an individual permission to perform specific clinical activities within a healthcare setting. It defines how a credentialed practitioner may be authorized to provide certain services outside their standard scope of practice, provided they work under appropriate supervision.
The privileging process establishes clear boundaries around what services a practitioner can deliver and under what conditions. Detailed privileging frameworks exist for different specialty areas, including orthotics, prosthetics, and pedorthics. For mastectomy-related services, specific privileging guidelines outline the requirements and supervision needed.
This structured approach to privileging ensures that practitioners provide safe, high-quality care while allowing for appropriate professional development under qualified supervision.
What is a Credentialing Committee?
A credentialing committee is a group of clinicians and administrators that reviews practitioners’ qualifications and decides whether to approve them to join a network or medical staff. The committee reviews licenses, board certifications, training, work history, malpractice history, and references, and then votes to approve, deny, or request more information. Hospitals and health plans each run their own committees, and payer committees commonly meet on a monthly schedule, which makes a complete file important.
What a Credentialing Committee Does
- Initial credentialing reviews applications from new practitioners who want to join the medical staff or a payer network.
- Reappointment re-evaluates current practitioners on a recurring cycle, every two to three years at most hospitals and at least every 36 months for payers under NCQA standards.
- Privileging decisions set the procedures and services each practitioner is qualified to perform, based on training and experience.
- Ongoing monitoring follows sanctions, complaints, and adverse events between review cycles.
Who Sits on the Committee
Hospital committees usually include physicians from several departments along with medical staff leaders and quality or risk representatives. Payer committees are typically made up of participating practitioners and medical directors. Members review files that credentialing specialists have already verified at the source, so the committee sees a finished file and focuses on judgment calls such as gaps in work history or past malpractice claims. The full workflow is covered in The Credentialing Committee Process, and the link between committee approval and clinical privileges is explained in hospital privileging for physicians.
How Do I Handle Out-of-Network Billing Situations?
Out-of-network (OON) billing occurs when you provide services to a patient whose insurance plan you don’t have a contract with. While these situations can be more complex than in-network billing, they can also be more profitable if handled correctly.
Key Steps for Out-of-Network Billing:
1. Verify Benefits and Set Expectations
Before providing services, verify the patient’s out-of-network benefits, including:
- Out-of-network deductible and whether it’s been met
- Coinsurance percentage (commonly 60-70% coverage vs 80-100% in-network)
- Out-of-network maximum out-of-pocket limit
- Whether the plan has out-of-network coverage at all (some HMOs and EPOs don’t)
Inform the patient in writing about their financial responsibility and obtain a signed acknowledgment.
2. Understand Your Billing Options
You have several approaches for OON billing:
- Balance Billing: You can bill patients for the difference between your charges and what insurance pays (except where prohibited by law or for emergency services under the No Surprises Act)
- Courtesy Billing: Submit claims to the insurance company on the patient’s behalf, but collect your full fee from the patient
- Self-Pay Arrangements: Offer discounted rates if the patient pays in full at time of service
3. Use Proper Claim Submission
- Submit claims using the CMS-1500 form with your full charges
- Include all required documentation
- Don’t use contracted rates; bill your standard (rack) rates
- Use appropriate modifiers if required by the payer
4. Payment Collection Strategy
- Collect estimated out-of-pocket costs upfront when possible
- Set clear payment policies for OON patients in your financial policy
- Send statements promptly when insurance processes the claim
- Offer payment plans for large balances
5. Appeal Underpayments
Insurance companies often underpay OON claims.
Don’t accept low payments without review:
- Compare payment to the usual and customary rate for your area
- Appeal if payment is unreasonably low
- Cite state prompt payment laws if applicable
- Consider balance billing the patient if appeals are unsuccessful
Important Legal Considerations:
- No Surprises Act: For emergency services and certain non-emergency services at in-network facilities, you cannot balance bill patients beyond in-network cost-sharing amounts
- State Balance Billing Laws: Some states restrict balance billing in specific situations
- Medicare/Medicaid: You generally cannot balance bill Medicare patients, and Medicaid prohibits it entirely
When to Accept OON Patients:
Consider these factors:
- Your practice’s payer mix and whether you can afford to see OON patients
- The patient’s ability to pay
- The complexity of the service and reimbursement potential
- Your capacity and whether OON patients displace in-network patients
Medwave can help you develop clear OON billing policies, verify benefits accurately, submit claims properly, and pursue maximum reimbursement while remaining compliant with all applicable laws.
What is Prior Authorization and How Does it Affect My Revenue Cycle?
Prior authorization (PA) is a cost-control process used by insurance companies that requires providers to obtain approval before performing certain services, procedures, or prescribing medications. The payer reviews the medical necessity of the proposed treatment before agreeing to cover it.
How Prior Authorization Affects Your Revenue Cycle
Prior authorization affects your practice’s revenue cycle in several ways.
- Services that need approval cannot be performed until it comes through, which can take anywhere from 24 hours to several weeks. That delays both the care and your ability to bill for it, and it leaves gaps in your revenue stream.
- Gathering clinical documentation, completing forms, making follow-up calls, and tracking approvals takes substantial staff time. That pulls people away from other revenue cycle work and raises operating costs.
- Performing a service without the required authorization is one of the most common reasons claims get denied. Even when the service was medically necessary, payers will deny a claim that lacks proper authorization, and you end up writing off the charge or billing the patient directly, which often leads to collection challenges.
- Patients who are ready for care can get frustrated by PA delays and may go elsewhere or abandon treatment altogether. That affects both your revenue and your practice’s reputation.
Best Practices to Minimize Impact:
- Maintain an updated list of services that require PA for each payer
- Verify PA requirements during insurance verification before scheduling
- Submit PA requests as early as possible with complete clinical documentation
- Track PA requests systematically and follow up promptly on pending approvals
- Train front-office staff to identify PA requirements during scheduling
- Consider working with a medical billing partner like Medwave that handles prior authorization for its billing clients
At Medwave, our billing team handles prior authorization requirements for the practices we work with, helping them avoid delays and denials while reducing administrative burden.
Can Medwave Help If I’m Joining an Existing Practice or Leaving One?
Yes, Medwave can assist with credentialing transitions when joining or leaving a practice. When joining a practice, we help ensure your individual credentialing is transferred or established correctly with all relevant payers, update NPI and provider enrollment information, and coordinate with the practice’s existing payer contracts to add you as a participating provider. When leaving a practice, we assist with notifying payers of your departure, establishing new contracts at your new location, transferring credentialing records, and ensuring continuity in your ability to bill for services. These transitions require careful timing and coordination to minimize gaps in your ability to see patients and receive reimbursement. We manage the administrative complexities so you can focus on patient care during these transitions.
What is the Difference Between a Claim Denial and a Claim Rejection?
A claim denial and a claim rejection differ in when the problem occurs. A rejection happens before adjudication, when the claim fails a technical check at the clearinghouse or the payer’s front end, and a denial happens after the payer has processed the claim and decided not to pay it. That timing decides what you do next.
Rejected Claims
A rejection means the payer never accepted the claim into its system. Typical causes are incorrect patient information, an invalid insurance ID, missing required fields, or formatting errors. Rejected claims come back quickly, usually within days, and carry no appeal rights because no coverage decision was made. Correct the error and resubmit. The payer treats a rejected claim as never received, so the timely filing clock keeps running and a fast correction matters.
Denied Claims
A denial comes with a reason code explaining why the payer will not pay, such as lack of medical necessity, a non-covered service, or exhausted benefits. Denials can be appealed, and each payer sets its own appeal deadline, so read the notice for the date. Some denials can be fixed with a corrected claim, while others need records and a written appeal.
Tracking rejections and denials separately shows where the revenue cycle is breaking down. Rejections point to front-end data entry and eligibility checks, and denials point to coding, documentation, and authorization. The full comparison is in the claim denial vs. rejection guide.
How Do Value-Based Care Contracts Differ from Traditional Fee-for-Service Contracts?
Traditional fee-for-service contracts pay providers based on the volume of services delivered, with each service having a set reimbursement rate. Value-based care contracts tie reimbursement to quality metrics, patient outcomes, and cost efficiency rather than just volume. In value-based arrangements, providers may receive bonuses for meeting quality benchmarks, shared savings for reducing overall healthcare costs, or penalties for poor outcomes. These contracts often include quality measures like patient satisfaction scores, preventive care rates, hospital readmission rates, and chronic disease management metrics. Value-based contracts typically require more robust data tracking and reporting capabilities. While they can increase revenue potential through performance bonuses, they also involve more risk and require investment in care coordination and quality improvement initiatives.
What is a Modifier in Medical Billing and When Should I Use One?
A modifier is a two-digit code added to a CPT or HCPCS code to provide additional information about the service performed without changing the basic definition of the procedure. Modifiers indicate circumstances such as bilateral procedures, multiple procedures during the same session, professional versus technical components, services performed by different providers, unusual circumstances, or distinct procedural services. Common modifiers include -25 (significant separately identifiable E&M service), -59 (distinct procedural service), -76 (repeat procedure by same physician), and -RT/-LT (right/left side). Using modifiers correctly is important for proper reimbursement, as they prevent claim denials, unbundling issues, and ensure you’re paid appropriately for the services provided. Incorrect modifier usage can result in denials or compliance issues.
What Should I Do If an Insurance Company is Consistently Underpaying Claims?
Consistent underpayment requires systematic investigation and action. First, document the pattern by comparing contracted rates to actual payments across multiple claims. Review your contract to confirm the agreed-upon fee schedule and payment terms. Common underpayment causes include outdated fee schedules in the payer’s system, incorrect contract loading, bundling of services that should be paid separately, or application of wrong payment policies. Contact the payer’s provider relations department with specific examples and documentation. File formal appeals for underpaid claims with detailed explanations of the correct payment amount. If the issue persists, consider involving your state’s insurance commissioner or seeking assistance from billing specialists who have experience negotiating with payers.
Do I Need Separate Malpractice Insurance for Telehealth Services?
Many traditional malpractice insurance policies now include telehealth coverage, but you should verify this explicitly with your insurance carrier. The coverage specifics can vary significantly, including whether it covers synchronous video visits, asynchronous consultations, phone consultations, and services provided across state lines. If you practice telehealth across multiple states, ensure your policy covers you in all states where you’re licensed and seeing patients. Some insurers offer telehealth endorsements or riders for an additional premium. As telehealth continues to evolve, review your malpractice coverage annually and document your telehealth policies and procedures. Having inadequate coverage for telehealth services could leave you personally liable in the event of a claim.
What is Medical Necessity and Why Do Claims Get Denied for Lack of It?
Medical necessity is the standard a payer uses to decide whether a service is appropriate and needed to diagnose or treat a patient’s condition, judged against accepted medical practice. A claim denied for lack of medical necessity means the payer reviewed the codes and the documentation and concluded the service lacked justification for that diagnosis, setting, or frequency.
How Payers Decide What Is Medically Necessary
Every payer applies its own clinical rules. Medicare uses National Coverage Determinations and Local Coverage Determinations, which list the diagnoses that support a given procedure. Commercial plans publish medical policies and often license outside criteria sets. In every case the review comes down to whether the diagnosis codes, the procedure codes, and the clinical note tell the same story.
Why Claims Get Denied for Lack of Medical Necessity
A handful of problems cause most of these denials.
- The diagnosis code does not support the procedure under the payer’s policy.
- The visit note leaves out the clinical detail that justifies the service.
- The service exceeds a frequency or quantity limit.
- The payer treats the service as experimental or investigational.
- The service needed prior authorization and none was obtained.
The wider denial picture is laid out in Top 12 Reasons Why Claims Get Denied.
How to Prevent Medical Necessity Denials
Write the reason for each service into the note itself, including symptoms, exam findings, treatments that already failed, and why the chosen service fits. Code to the highest ICD-10-CM specificity the note supports so the diagnosis pairs cleanly with the procedure. Check the payer’s policy or the Medicare coverage database before ordering expensive or frequently repeated services. For Medicare patients, an Advance Beneficiary Notice of Noncoverage lets the patient agree in advance to pay when Medicare is expected to deny a service as not reasonable and necessary, and modifier GA tells the payer the notice is on file.
What to Do After a Medical Necessity Denial
Start with the denial reason and remark codes, since they usually name the missing element. Gather the full record, then write a letter of medical necessity that ties the diagnosis, findings, and treatment to the payer’s own criteria. File the appeal before the deadline printed on the denial notice. Some payers also offer a peer-to-peer call with a medical director, which can settle a denial faster than a written appeal. The guide to writing a medical claim appeal letter covers the letter itself.
How Long Do Insurance Companies Have to Pay Claims?
How long insurance companies have to pay claims depends on the payer and the state. Medicare sets a 30-day ceiling for clean claims, and interest is owed on a payable clean claim that is still unpaid after that. Medicare also has a payment floor, so a contractor will not release payment before day 14 for electronic claims or day 29 for paper claims.
Commercial payers follow state prompt payment laws, and the deadlines vary. Many states fall between 30 and 45 days for a clean claim, some set shorter windows for electronic submissions, and some add statutory interest or penalties for late payment. Self-funded employer plans are generally exempt from state prompt payment laws and follow federal claims rules and their own plan documents.
The clock starts only when the payer receives a clean claim. A claim with missing information, a coding error, or an open request for records does not start it until the payer has what it needs. Submitting claims that pass the first time is the most direct way to get paid inside the window, and your clean claim rate shows how many of your claims qualify.
Payer contracts can set their own payment terms, usually in a timely payment clause, and those terms often match or shorten the legal minimum. Read the contract for the deadline, the interest rate on late payment, and the way the payer defines a clean claim. The guide to payer contract analysis shows where payment terms sit in a typical agreement.
When a payer misses its deadline, note the date it received the claim, cite the state statute or the contract clause, and request payment with any interest owed. Keep the clearinghouse confirmation as proof of receipt.
What Clean Claim Rate Should My Practice Aim For?
A clean claim rate of 95% or higher is considered excellent in the medical billing industry. Clean claims are those submitted correctly the first time without errors, requiring no additional information or corrections before processing. The industry average is typically between 75-85%, meaning there’s significant room for improvement in many practices. Low clean claim rates lead to delayed payments, increased administrative costs, and reduced revenue. Factors that impact your clean claim rate include accurate coding, complete patient information, proper documentation, timely filing, and understanding payer-specific requirements. Professional billing services often achieve higher clean claim rates through dedicated quality control processes, coding expertise, and familiarity with payer requirements.
What is the National Provider Identifier (NPI) and Do I Need One?
The National Provider Identifier (NPI) is a unique 10-digit number that identifies a healthcare provider in HIPAA standard transactions such as claims. CMS administers it through the National Plan and Provider Enumeration System (NPPES), and getting one is free. Any provider who bills Medicare, Medicaid, or most commercial insurers needs an NPI, and every claim must carry it.
There are two types. A Type 1 NPI belongs to an individual provider, such as a physician, nurse practitioner, or therapist. A Type 2 NPI belongs to an organization, such as a group practice, clinic, or billing entity. A provider who incorporates a practice may need both, and the choice of which to bill under is covered in group NPI or individual NPI.
An NPI is assigned once and stays with the provider for a career, across employers, locations, and specialty changes. The number carries no information about licenses or credentials. The NPPES record behind it, including the practice address and taxonomy code, must be kept current, and HIPAA requires changes to be reported within 30 days. Mismatched NPPES, CAQH, and enrollment data is a common cause of credentialing and claim delays.
You need an NPI before you can enroll with Medicare or credential with commercial payers. For the Medicare side, see How to Get Credentialed with Medicare.
How Does Moving to a New State Affect My Credentialing and Payer Contracts?
Moving to a new state significantly impacts your credentialing because you’ll need a medical license in the new state before practicing there. You must notify all insurance companies and healthcare facilities where you’re credentialed about your practice location change. Most payer contracts are state-specific, so you’ll likely need to initiate new credentialing applications in your new state rather than simply transferring existing contracts. This process can take 90-180 days, so plan ahead and start the new state licensing and credentialing process well before your move. You may also need to update your CAQH profile, NPI information, DEA registration, and malpractice insurance for the new location.
What is the Difference Between Credentialing and Privileging?
Credentialing verifies that you have the appropriate education, training, licenses, and competence to provide medical care. Privileging grants you permission to perform specific procedures or provide particular services at a healthcare facility. While credentialing confirms you’re a qualified physician, privileging determines exactly what you’re allowed to do at a specific location. For example, a surgeon may be credentialed as a qualified physician but privileged to perform only certain types of surgeries based on training and experience. Hospitals and surgical centers conduct privileging as a separate process after credentialing, reviewing your training, experience, and outcomes for specific procedures you wish to perform.
Can I Bill Insurance Companies While My Credentialing is in Progress?
Generally, you cannot bill insurance companies as an in-network provider until your credentialing is fully approved and effective. However, you may be able to see patients and bill them as self-pay or out-of-network during this period. Some insurance companies offer “interim” or “temporary” credentialing that allows you to begin seeing patients while full credentialing is being processed, though this is not universal. Once your credentialing is approved, some payers allow retroactive billing back to your application date or effective date, but this varies significantly by payer and contract terms. Check each payer’s specific policies and inform patients about their potential financial responsibility during the credentialing period.
What does a DataSpring CAQH application error actually cost in lost revenue?
For a physician with average annual billings of $200,000, a three-month credentialing delay caused by a CAQH error works out to roughly $50,000 in non-billable revenue. At $250,000 in annual billings, that same three-month delay costs closer to $62,500. Beyond the direct revenue loss, staff typically spend 20 to 40 hours per provider tracking down missing documents and following up on stalled applications, adding $500 to $1,000 in labor costs on top of the lost billing. The most expensive mistake is a missed attestation, since some insurance companies treat a lapsed profile as a withdrawn application, which can restart the entire credentialing process and add three to six months to the timeline.
What Happens if My Credentialing Application is Denied?
If your credentialing application is denied, you’ll typically receive written notice explaining the reasons for denial. Common reasons include incomplete documentation, licensing issues, malpractice history, or gaps in work history that weren’t adequately explained. You have the right to appeal the decision by providing additional documentation or clarification. The appeals process varies by organization but usually involves submitting a formal written appeal within 30-60 days. Working with credentialing specialists can help you understand the denial reasons, gather appropriate documentation, and navigate the appeals process effectively. In some cases, you may need to wait a specified period before reapplying.
What Common Mistakes Should I Avoid During the Credentialing Process?
Key mistakes include submitting incomplete applications with missing signatures or documents, providing outdated or expired documentation, failing to disclose required information (gaps in employment, malpractice claims, disciplinary actions), not responding promptly to requests for additional information, and missing critical deadlines. Also, avoid using inconsistent information across different applications, neglecting to maintain current contact information with credentialing organizations, and failing to track renewal dates for licenses and certifications. Consider using credentialing services to help manage the complex requirements and timelines across multiple organizations.
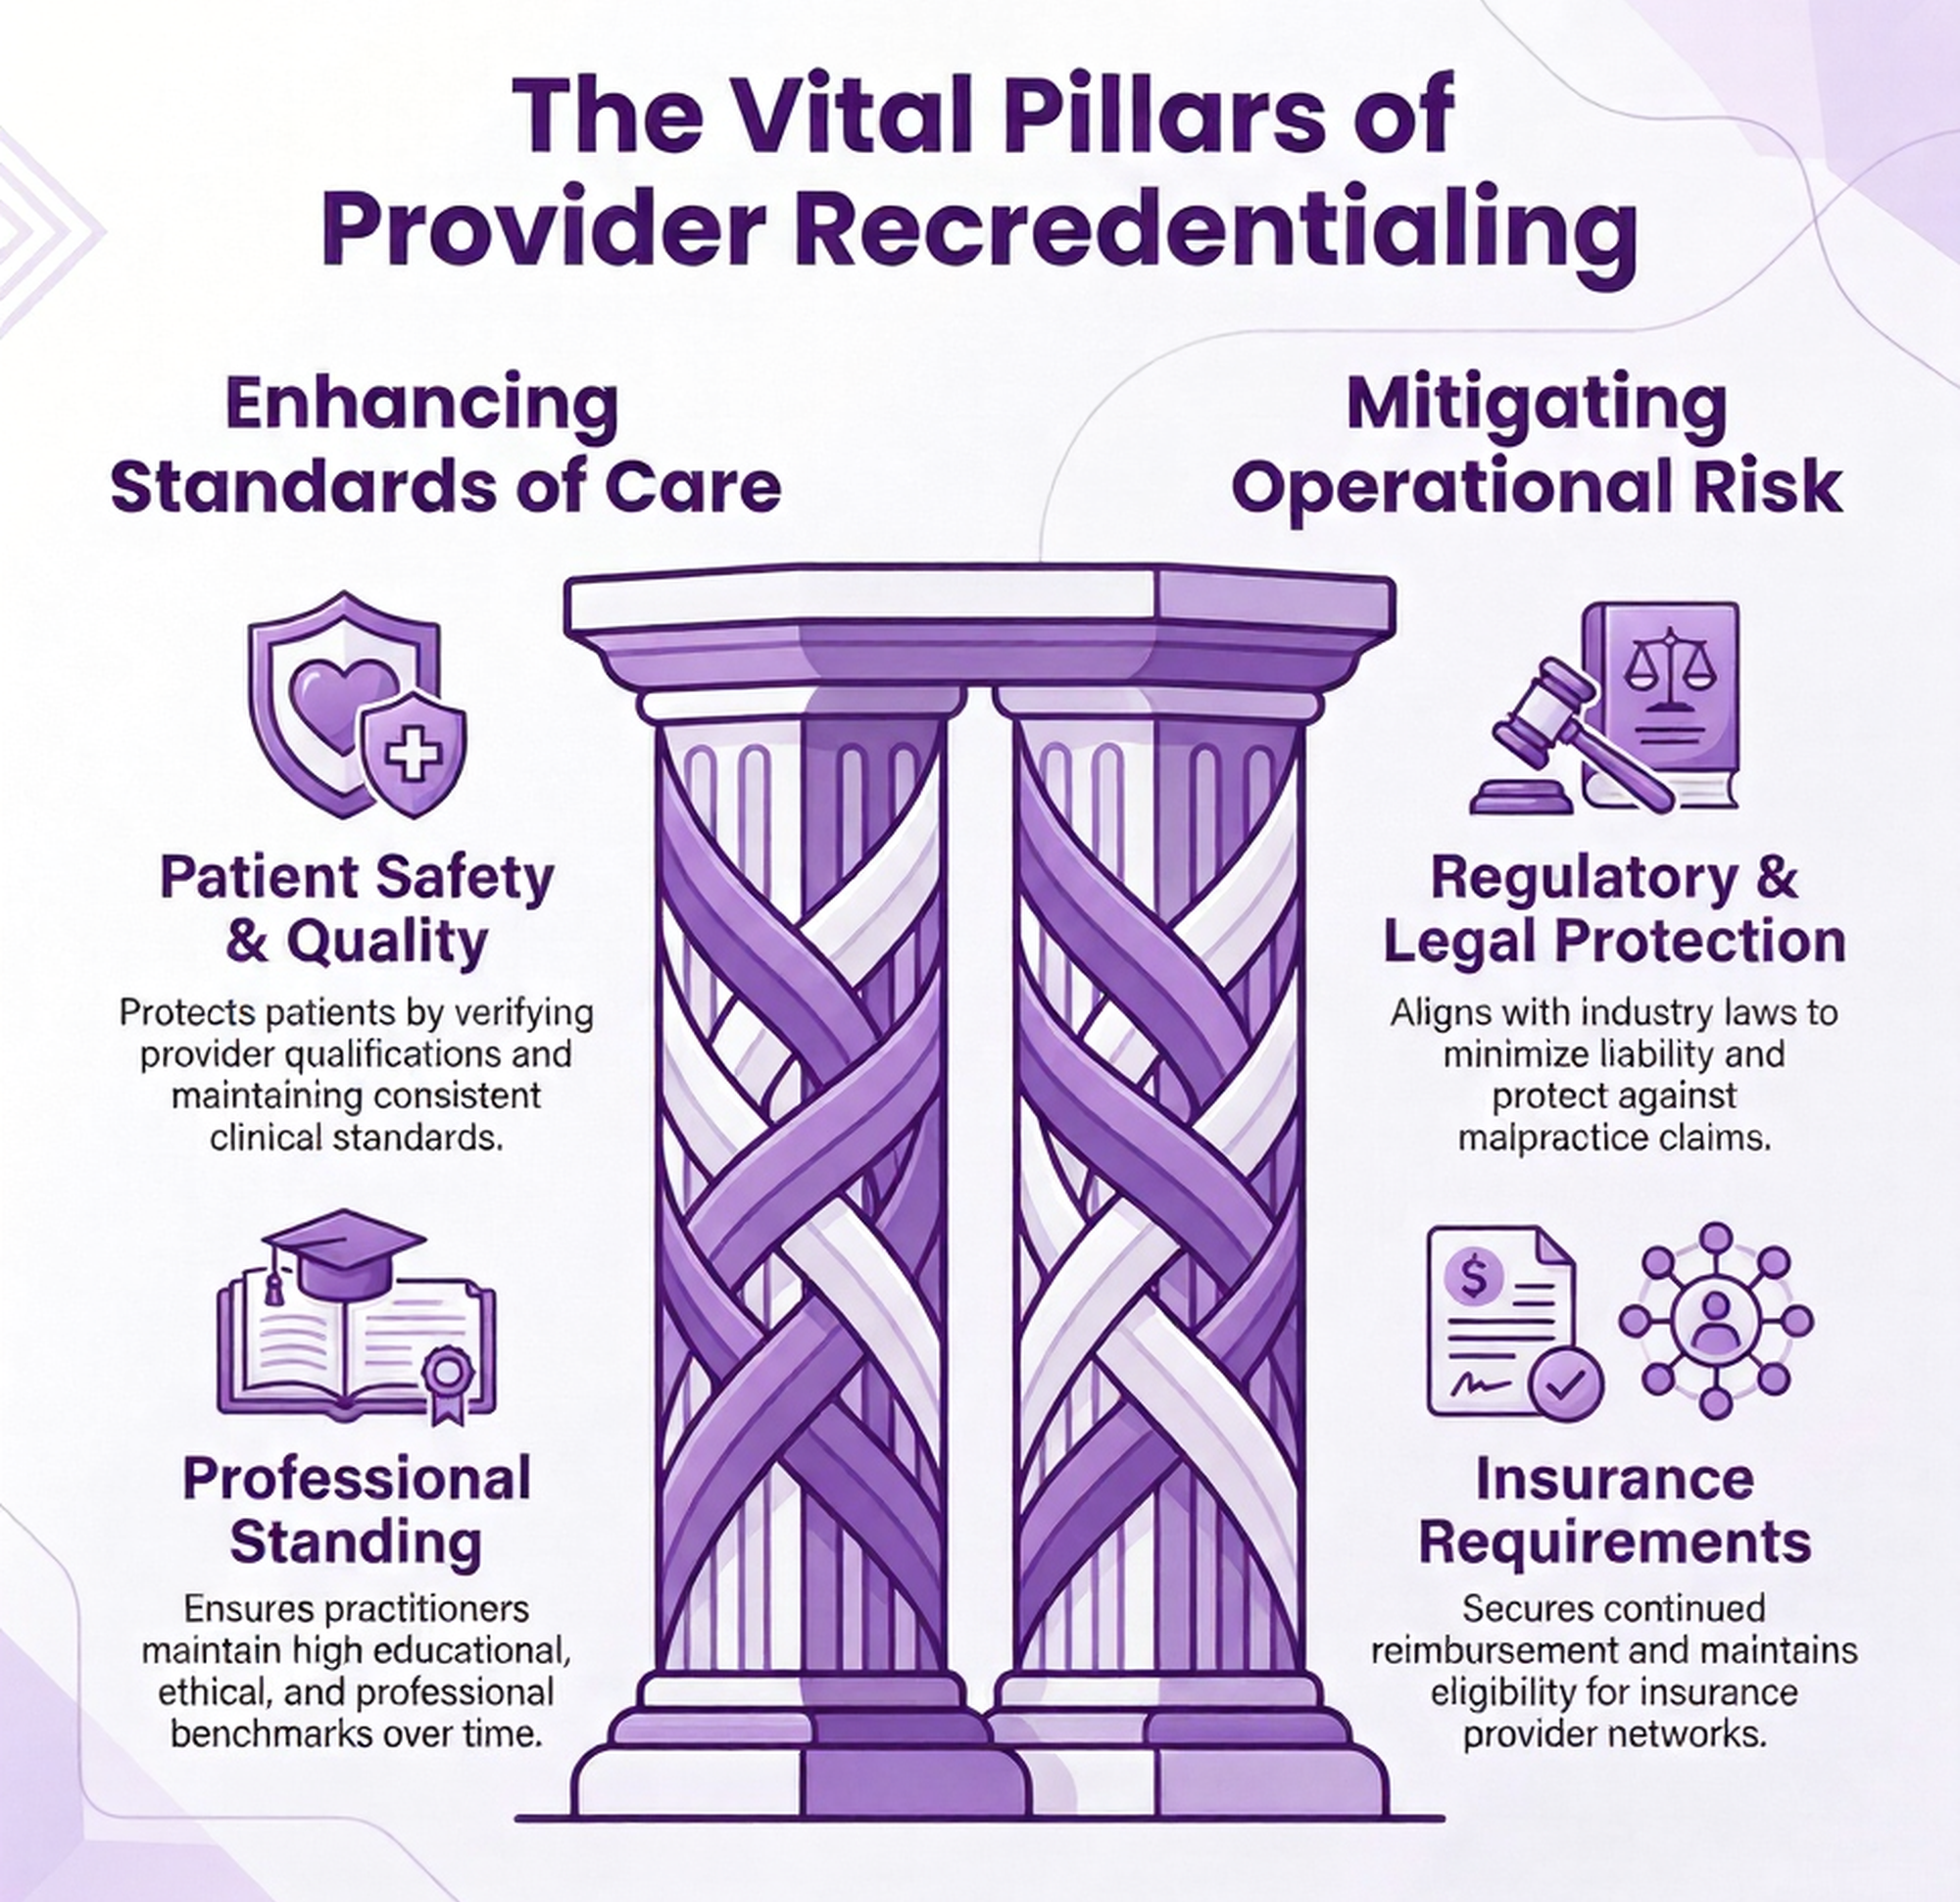
What is Recredentialing and How Often Does it Occur?
Recredentialing is the periodic re-verification of a provider’s credentials by the payer, hospital, or other organization that first credentialed them. Payers following NCQA standards recredential at least every 36 months from the last credentialing decision. Hospitals reappoint their medical staff on a separate cycle. The Joint Commission has allowed a three-year reappointment cycle since late 2022, though many hospitals keep a two-year cycle and some states require it by law.
The review covers much of the same ground as the first application. The organization re-verifies the state license, DEA registration, board certification, and malpractice coverage, checks sanction and exclusion lists, and asks about new claims, disciplinary actions, or changes in privileges. It also looks at performance data such as peer review results and quality metrics, which an initial application does not have.
CAQH (now DataSpring, powered by CAQH) runs on a faster clock. The profile must be re-attested at least every 120 days, or every 180 days in Illinois, and payers pull much of their recredentialing data from it. Keep licenses, practice locations, and insurance current as they change, and answer each payer’s recredentialing notice promptly. A missed deadline can mean suspended privileges or removal from a payer panel, which interrupts in-network payment.
More detail is on the recredentialing service page. The article on staying credentialed walks through the process step by step, and Medicare revalidation follows its own schedule.
What Documents and Information Do I Need to Prepare for Credentialing?
Essential documents include current medical license(s), DEA registration, board certifications, CV with complete work history, medical school diploma and transcripts, residency and fellowship certificates, malpractice insurance declarations page, hospital privileges documentation, and Medicare/Medicaid enrollment information. You’ll also need to provide references from colleagues, complete background check authorizations, and may need additional specialty-specific certifications. Keep digital copies organized and ensure all documents are current, expired items will delay the process.
What Happens if I Want to Terminate a Payer Contract or if a Payer Terminates Me?
Contract termination typically requires advance notice (usually 90-180 days) as specified in the agreement. If you initiate termination, you’ll need to notify affected patients and help them transition care or understand their options. You remain obligated to complete care for patients with ongoing treatment needs during the notice period. If a payer terminates your contract, they must provide adequate notice to patients and may need to continue covering your services for patients with ongoing episodes of care. Always review termination clauses carefully and consider the impact on your patient base and revenue before making termination decisions.
Can I Negotiate Better Rates with Insurance Companies, and What Leverage Do I Have?
Yes, rate negotiation is often possible, especially if you can demonstrate value to the payer. Your leverage may include unique specialties or services in your area, strong quality outcomes and patient satisfaction scores, efficient care delivery and lower per-episode costs, significant patient volume or market presence, and willingness to participate in value-based care programs. Smaller practices can sometimes gain leverage by joining provider networks or working with consultants who specialize in payer negotiations.
What Key Terms Should I Focus on When Negotiating Payer Contracts?
Critical contract terms include reimbursement rates and fee schedules, covered services and exclusions, prior authorization requirements, claims submission and payment timelines, quality metrics and performance standards, termination clauses and notice periods, and administrative requirements like electronic health record integration. Pay special attention to “holdback” provisions where payers retain a percentage of payments, and ensure you understand any risk-sharing arrangements or value-based care components.
How Long Does the Typical Payer Contracting Process Take?
The payer contracting timeline varies significantly depending on the payer, provider type, and complexity of services offered. Initial contracts with major commercial payers typically take 90-180 days from application submission to final execution. Government payers like Medicare and Medicaid may have shorter timelines (30-90 days) but involve different enrollment processes. Factors that can extend timelines include incomplete applications, credentialing requirements, site visits, and back-and-forth negotiations on contract terms.
What is Payer Contracting and Why is it Important for Healthcare Providers?
Payer contracting is the process of negotiating and establishing formal agreements between healthcare providers and insurance companies or other payers that define reimbursement rates, covered services, quality metrics, and administrative requirements. These contracts are crucial because they directly impact your revenue, determine which patients you can serve, and establish the terms under which you’ll be paid for services. Without proper contracts, providers may face reduced reimbursement rates, payment delays, or limited patient access.
How Important is Medical Credentialing to a Healthcare Provider?
Medical credentialing is a process by which medical organizations verify the credentials of healthcare providers to ensure they have the required licenses, certification and skills to properly care for patients. It’s an essential function for hospitals and others which precedes hiring or obtaining coverage by an insurance carrier. Medical credentialing is perhaps most important because it’s the one method that permits patients to place their trust with utmost confidence in their chosen healthcare provider(s). Through a standardized process involving data collection, primary source verification and committee review by health insurance plans, hospitals and other healthcare agencies, patients are confident in their healthcare professional’s ability and experience.
Do You Support Healthcare Providers that Perform Telehealth / Telemedicine?
Yes, we support medical providers who perform telehealth / telemedicine services. Virtual visits are an excellent way to boost your offices productivity and maintain your patient count. We can work with your established telehealth billing platform or help you set up a new one.
What is Medical Billing?
Medical billing is the process in which medical providers are paid for performing procedures. The procedures are coded using the most current CPT and ICD-10 codes. The codes are then sent to the insurance companies on the proper HCFA 1500 forms for review and payment. It is the responsibility of the medical biller and coder to make sure the claim is coded correctly, submitted in a timely manner and paid to the physician. Reducing spend is the primary reason that medical practices elect to outsource their medical billing to a third-party provider.
What is Medical Credentialing?
Medical Credentialing is the process of contracting with Insurance companies in order to become an in-network or approved medical provider for that company. Becoming a participating provider for insurance companies in your area is an extremely important part of any medical practice. Whichever companies you are contracted with will dictate which patients you are allowed to treat and what your reimbursement rates will be.
What Type(s) of Family Practice Medical Billing Services Do We Offer?
Medwave provides medical billing and credentialing built around the day-to-day mix a family practice actually sees, routine E/M visits (99213, 99214), annual wellness exams, chronic disease management, immunizations, and common in-office procedures.
We handle claim submission and follow-up for the coding situations that trip up family practices most often, including correctly billing a wellness visit and a problem-focused visit on the same date with modifier -25, applying preventive care and screening codes accurately, and managing the E/M level selection that drives a large share of primary care reimbursement.
Beyond billing, we manage credentialing and payer contracting specific to primary care networks, track prior authorizations for referrals and specialist coordination, and run denial management tuned to the claim volume and visit frequency typical of a busy family practice.
What Insurers Have We Worked with in the Past?
Medwave Billing & Credentialing and its educated team of experts have worked with multiple commercial and government insurances.
We’ve worked with the following insurers:
- Aetna
- AARP
- Align Network
- Amerihealth
- Anthem BCBS
- Assurant Health
- CHIP
- Cigna
- Consumers Life Insurance Company
- Coventry One
- Freedom Blue
- Geisinger Health Plan
- Health America
- Health Net
- Highmark BCBS
- Horizon BCBS
- Humana
- Independence BCBS
- Magellan
- Medical Mutual of Ohio
- Medicaid
- Medicare, Novitas Solutions
- Optum Health
- Oxford Health Plans
- Premiere Comp Solutions
- Security Blue
- United Healthcare
- UPMC
- UPMC for You
- VBH
- Veterans Association
What are Our Rates?
Medwave and its team of medical billing and credentialing specialists understand the time and effort it takes to run an efficient medical office. That is why every office receives specialized attention and a custom plan to help your practice succeed. Every contract is priced according to the needs of your practice and is always based upon volume.
What Types of Medical Practices do We Serve?
Although not limited to (as we have done practices outside of these), we typically serve the following medical practices: Behavioral Health, Durable Medical Equipment (DME), Toxicology Labs, Speech Therapy, Genetic Testing Labs, Substance Abuse, Chiropractic, Occupational Therapy, Family Practice, Internal Medicine, Physical Therapy, Holistic Therapy, Sleep Study Labs, Transportation, Medical Cannabis, etc.
Do You Support Cannabis Medicine with their Billing Requirements?
*Currently, most major insurers and Medicaid / Medicare do not cover medical marijuana treatment, since cannabis is a controlled substance on the federal level. However, if you’re a medical marijuana provider and perform services that are covered by the aforementioned insurers (no matter what they are), then reach out to us. We’ve helped a number of groups get credentialed and bill for internal, alternative services.
Do You Support Genetic Testing Labs with their Billing Needs?
Yes, we provide genetic testing lab billing services. Our team is experienced and well educated in the medical billing and coding guidelines of genetic testing lab specialists and has firsthand experience working with commercial and government companies to get your claims paid fast and efficiently.
Do You Fix Denied Medical Claims?
Yes, once you contractually sign with us and we start your medical billing, we will analyze past claims as well. Those denied medical claims can be fixed and you will be paid out on them.
Is A/R Recovery Part of Your Services?
Yes, Accounts receivables (AR) recovery is part of our services. In the last 16 years, our firm has resolved more than $100 million worth of insurance claims, in getting insurance companies to reimburse the amount due to health care providers.
Which Regions do We Serve w/ Billing & Credentialing Service?
Although we serve the entire United States, we target the Greater Pittsburgh Region. Managing billing and credentialing across multiple U.S. healthcare regions means knowing the rules where your providers practice, beyond the federal baseline.
Outside of the Pittsburgh region, we service many billing, contracting regions etc,.
What’s Your Medical Credentialing On-Board Protocol?
Providers and hospitals have many questions in reference to on-board medical credentialing protocol(s). The following blog post, Credentialing (On-Board Process for Providers, Facilities) discusses our overall protocol in detail.
Do You Partner with 3rd Party Medical Groups?
Medwave does partner with a number of 3rd party groups, especially medical product sales groups that have medical provider clients in need of credentialing and billing.
Do You Provide Billing and / or Credentialing to Laboratories?
Medwave does provide billing and credentialing to laboratories of all types, but specifically Sleep Study Labs, Genetic Testing Labs and Toxicology Labs.
Laboratory billing carries its own set of challenges that differ from standard provider billing. These include high claim volume, payer-specific medical necessity requirements, and coding rules that vary significantly by test type and specimen source. We manage the CPT and HCPCS coding specific to each lab specialty, track prior authorization requirements that many payers impose on genetic and toxicology panels, and handle the documentation needed to support medical necessity on tests that are frequently scrutinized or denied.
On the credentialing side, we help laboratories get contracted with commercial and government payers, maintain CLIA compliance documentation as part of the credentialing file, and manage the recredentialing cycle so lab licenses and certifications don’t lapse mid-contract. For labs processing high volumes of specimens across multiple referring physicians, we also help structure billing workflows that keep pace with throughput without sacrificing clean claim rates.